What’s the Anion Gap?
The anion gap is a computed value from routine electrolytes that helps clinicians understand a patient’s acid-base balance. It is usually derived from sodium, chloride, and bicarbonate, and sometimes includes potassium depending on the formula used. In simple terms, the anion gap helps reveal unmeasured charged particles in the blood that can point to a metabolic acidosis or another acid-base disorder.
In a newborn or neonate, this number is read differently than in older children or adults because neonatal physiology is still adapting after birth. A newborn’s serum chemistry changes quickly during the first days of life, so the anion gap calculation must be viewed as part of the full picture, not as a stand-alone diagnostic marker.
The idea behind the anion gap is tied to the body’s buffer system. When acids build up or bicarbonate is lowered, the numbers shift, and the gap may rise. When chloride goes up or albumin falls, the gap may decrease. That is why understanding the relationship between serum sodium and serum chloride matters so much in neonatal assessment.
Expected Anion Gap Range in Newborns
The normal reference range for the anion gap in newborns can differ by laboratory, age after birth, and the formula used. In numerous settings, the expected value is modestly different from adult values, especially in the initial days of life. A neonatal reference interval should always be assessed using the lab’s own standards when available.
For newborn lab values, a normal anion gap is often viewed to be in a broad low-to-mid range, but the exact cutoff depends on whether potassium is included and how the lab measures electrolytes. Because serum bicarbonate can also vary during early adaptation, a single number is not as important than the trend and the clinical picture.
A newborn may have a borderline or mildly altered gap without having a dangerous condition. However, if the anion gap is clearly elevated, clinicians often evaluate for metabolic acidosis and search for an underlying cause. Likewise, a low gap may suggest low albumin, excess chloride, or a testing issue.
It is important to remember that the normal range is not universal. A premature infant, a sick neonate, or a baby with abnormal hydration status may have values that vary from a healthy term infant. For that reason, clinical interpretation should always include age, feeding status, respiratory status, and the rest of the serum chemistry panel.
What the Anion Gap Calculator Operates
An Anion Gap Calculator applies measured electrolyte values to calculate the unmeasured anions in the blood. The most common formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Some calculators also include serum potassium:
Anion gap = (serum sodium + potassium) - (serum chloride + serum bicarbonate)
The result is an effective screening tool, especially when evaluating acid retention or a potential acid-base disturbance. In newborn care, the calculator is often used alongside a blood gas, a pH measurement, and the bicarbonate level to evaluate the infant’s condition more completely.
Albumin matters too. Because albumin is a major unmeasured anion, low albumin can make the gap look falsely normal or low. That is why a calculator may be helpful, but it does not replace professional interpretation. In a baby with illness, the same numeric result can mean something very different depending on hydration, renal status, and the presence of systemic illness.
Useful reminder: the anion gap is a clue, not a diagnosis. In newborns, it works best when paired with the blood gas, pH, bicarbonate level, and overall clinical context.
Why Newborn Anion Gap Values Can Differ From Adults
Multiple features of neonatal physiology account for why newborn values can vary from adult values. After birth, the infant shifts from placental support to independent breathing, circulation, and kidney function. This rapid shift affects electrolyte handling and acid-base balance.
Prematurity can make these variations more apparent. A premature infant may have underdeveloped kidneys, reduced acid excretion, and less consistent buffering capacity. Because of this, the same serum chemistry pattern may have a different meaning than it would in an older child. The growing kidney plays a major role in chloride reabsorption, bicarbonate conservation, and overall electrolyte balance.
Kidney function matters greatly in the early neonatal days. A newborn kidney is still learning to control sodium levels, chloride levels, fluid, and acid balance. This may affect the Anion Gap Calculator and other laboratory results. A brief change is not always a sign of disease, but persistent abnormalities deserve attention.
Newborns also have significant changes in fluid balance, feeding patterns, and metabolic function. These variations can alter the buffer balance and the chloride shift. Consequently, pediatric interpretation relies on age-specific reference interval data rather than adult assumptions. A elevated anion gap or low anion gap should be interpreted as part of a more comprehensive metabolic evaluation.
Common Causes of a High Anion Gap in Newborns
A high anion gap in a newborn often indicates the build-up of additional acids in the blood. This is a important finding in metabolic acidosis and can signal a serious problem that requires prompt evaluation. The most common causes include:
- Lactic acidosis, often related to poor oxygen delivery, poor circulation, or severe illness Sepsis, which can cause tissue hypoperfusion and systemic illness Ketoacidosis, less common in newborns but possible in certain metabolic or feeding-related states Inborn errors of metabolism, which may interfere with normal acid handling and energy production
Lactic acidosis is a serious concern because it can reflect inadequate oxygen delivery or impaired perfusion. In a sick newborn, this may occur with infection, respiratory compromise, or circulatory instability. The anion gap rises because lactate is an unmeasured anion that builds up in the bloodstream.
Sepsis is another critical cause. A newborn with sepsis may show poor feeding, temperature instability, lethargy, abnormal breathing, or worsening lab results. The acid-base disorder may be subtle at first, so the anion gap can provide an initial clue that something is wrong.
Inborn errors of metabolism are especially important in neonatal evaluation because they may present with a high anion gap before the diagnosis is obvious. These disorders can cause acid retention, abnormal ammonia levels, or worsening metabolic disturbance after feeding starts. When the gap is elevated without a clear explanation, clinicians often expand testing quickly.
Ketoacidosis is less common in a newborn than in older patients, but it can occur in specific settings where energy metabolism is disrupted. Regardless of the cause, a high gap should be treated as a signal to investigate the full clinical picture rather than as an isolated number.
Typical Causes of a Standard or Low Anion Gap
A regular anion gap does not always mean all is well, and a low anion gap can be informative. In neonates, the most common reasons include hypoalbuminemia, hyperchloremia, or a testing issue such as lab error.
Hypoalbuminemia is notable because albumin contributes to the measured equilibrium of charged particles. If protein levels are decreased, the gap may be lowered even when another process is present. This can make interpretation tricky, especially if the baby is ill or has fluid shifts that reduce blood proteins.
Hyperchloremia can also decrease the anion gap. When chloride rises compared with sodium and bicarbonate, the calculated gap decreases. This can happen after certain IV fluids, with renal handling changes, or during certain acid-base disturbances. In some cases, the pattern may suggest a normal-gap metabolic acidosis rather than a high-gap disorder.
https://anion-gap-calculator272.lowescouponn.com/can-potassium-be-included-in-the-anion-gap-calculationLab error should always be considered if the result does not fit the infant’s condition. Repeating the test may be appropriate if the values are unexpected, especially when the baby looks clinically well or the numbers conflict with the blood gas. A mismatch between the anion gap and the overall serum chemistry can point to sampling problems or analytical variation.
When the anion gap is within range, it does not fully exclude disease. A newborn can still have serious illness, especially if the bicarbonate level is low or the blood gas shows abnormal pH. That is why the gap should be used as one part of a larger metabolic evaluation.
How to Read Results Safely
Accurate reading starts with the blood gas, pH, and bicarbonate as a group. A single number cannot define a diagnosis. The anion gap helps classify an acid–base disorder, but it must be paired with the baby’s signs, feeding pattern, breathing effort, and other lab results.
If the bicarbonate level is low and the pH is acidemic, the clinician looks closely at the gap to see whether the acidosis is increased-gap or standard-gap in nature. A high gap may suggest lactic acid, ketones, toxins, or metabolic disease. A normal gap may suggest bicarbonate loss or chloride gain. Either pattern can be important in a newborn.
Clinical context is more important than any single cutoff. A baby with mild lab changes but normal activity and feeding may be monitored differently than a baby with poor perfusion, respiratory distress, or signs of infection. The same numeric result can have different meaning depending on age in hours, hydration, and whether the infant is premature.
If the result is unexpected, clinicians may repeat the serum chemistry, review the collection method, and compare it with the blood gas. This helps determine whether the abnormality is real and whether it reflects a true metabolic disturbance or a measurement issue. For newborn care, accurate interpretation is part of careful neonatal assessment, not just formula use.
When to Obtain Immediate Medical Review
Immediate medical review is required when a newborn has worrisome symptoms plus abnormal lab results. Warning signs include respiratory distress, poor feeding, lethargy, and dehydration. These symptoms may indicate a systemic illness, infection, poor perfusion, or a serious metabolic problem.
Respiratory distress may appear as rapid breathing, grunting, flaring nostrils, or chest retractions. This can affect acid-base balance and may be accompanied by a rising anion gap or abnormal pH.
Poor feeding and lethargy are especially important in a neonate because they can be early signs of sepsis or inborn errors of metabolism. If a newborn is slow to rouse, feeds poorly, or becomes less responsive, immediate evaluation is warranted.
Dehydration can also shift electrolyte patterns and worsen acid retention. Signs may include decreased urine output, dry mucous membranes, or excessive weight loss. In some cases, dehydration contributes to both clinical instability and altered serum chemistry.
If symptoms are present, do not depend on the anion gap alone. A prompt blood gas, pH assessment, repeat electrolytes, and broader metabolic evaluation may be needed. This is especially true when prematurity, renal function concerns, or suspected infection are part of the picture.
Common Questions
What is the typical anion gap in newborns?
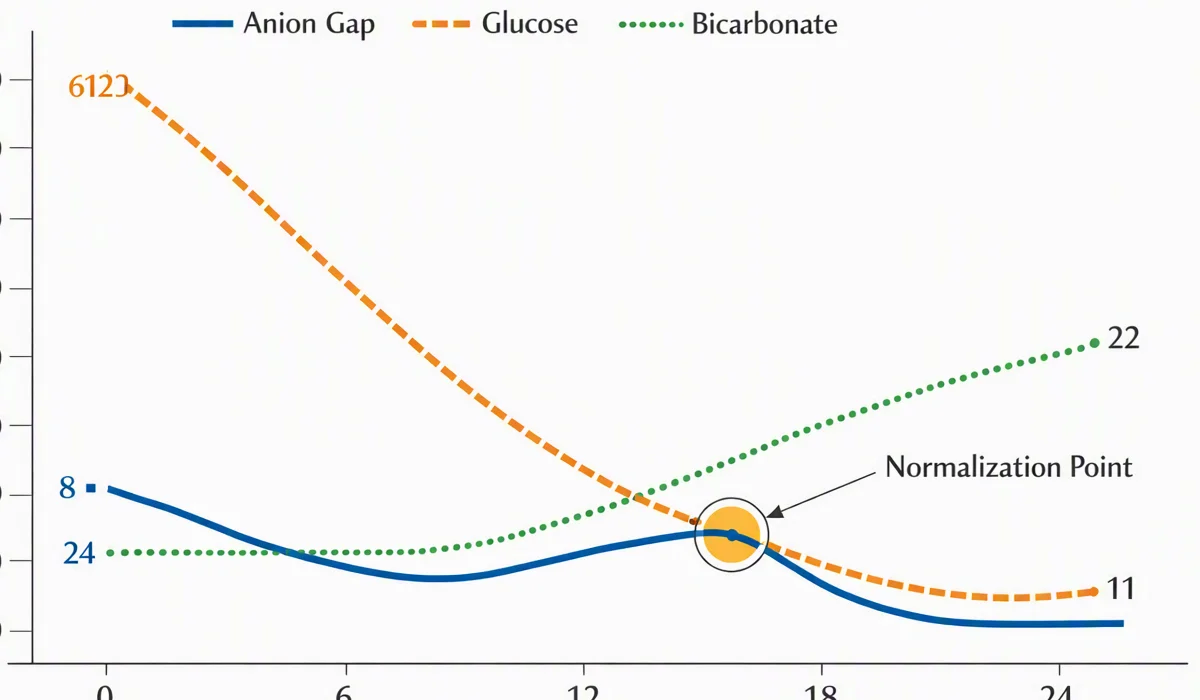
The expected anion gap in newborns depends on the lab’s reference range, the calculation formula, and the baby’s age after birth. Many newborn lab values fall within a larger reference interval than adult values. Because serum bicarbonate and other electrolytes shift quickly in early life, the best interpretation uses the lab’s own reference range plus the newborn’s clinical status.
Is the expected anion gap in newborns different from adults?
Yes. The typical anion gap in newborns can differ from adults because of neonatal physiology, prematurity, and immature renal function. Newborns are still adjusting their acid-base balance, so pediatric interpretation should use age-appropriate standards rather than adult assumptions.
How do you utilize an Anion Gap Calculator for a newborn?
An Anion Gap Calculator relies on serum sodium, serum chloride, and serum bicarbonate, and in some cases potassium, to estimate the gap. For newborns, it should be used alongside albumin, a blood gas, and the bicarbonate level. The result assists guide clinical interpretation, but it does not take the place of a full neonatal assessment.
What does a high anion gap mean in a newborn?
A high anion gap in a newborn may suggest unmeasured acids in the blood and may point to metabolic acidosis. Common causes include lactic acidosis, sepsis, ketoacidosis, and inborn errors of metabolism. Because these can be serious, a high gap should always be evaluated in clinical context.
Can a normal anion gap still be serious in a newborn?
Yes. A normal anion gap does not rule out illness. A newborn can still have respiratory distress, sepsis, dehydration, or another acid-base disorder with a normal gap. That is why blood gas results, pH, bicarbonate, and the overall clinical picture are vital for safe interpretation.