An Anion Gap Calculator is a practical tool for interpreting an anion gap result on a metabolic panel. It aids in turning common laboratory values into a reliable diagnostic clue for assessing acid-base balance, especially when a clinician is looking over an electrolyte panel for signs of metabolic acidosis or related acid-base disorder patterns.
When used properly, the calculator does more than provide a number. It helps relate serum sodium, serum chloride, and serum bicarbonate to the broader picture of metabolic panel interpretation. That means it can support recognition of a high anion gap, a low anion gap, or results that need confirmation with additional testing.
Explaining the Anion Gap Measures
The anion gap is an estimate of the difference between measured positive and anions electrolytes in the blood. In daily practice, it mainly shows the relationship between sodium, chloride, and bicarbonate. Because not all electrically charged particles are directly measured, the anion gap provides an indirect look at the presence of unmeasured ions and unmeasured anions.
In simple terms, the anion gap helps reveal whether something is affecting acid-base balance. A normal result indicates that the measured cations and anions are in expected proportion, while an abnormal result may indicate an underlying acid-base disorder. This is why the anion gap is a standard part of metabolic panel interpretation in many contexts.
Although the number is derived from routine chemistry tests, its clinical significance is much wider than the formula itself. A change in the anion gap can be a diagnostic clue that triggers a more detailed metabolic acidosis evaluation, review of medications, or follow-up testing such as a blood gas.
How to Work Out the Anion Gap
An Anion Gap Calculator simplifies the process of calculate anion gap from results on a basic metabolic panel or comprehensive metabolic panel. The standard anion gap formula is:
Anion gap = Sodium - (Chloride + Bicarbonate)
Some labs may use small variations of formulas, especially if potassium is included. But, the sodium-based version is the most common in everyday interpretation.
To use the calculator, enter the patient’s serum sodium, serum chloride, and serum bicarbonate. The result estimates the gap between measured cations and anions. If the number is higher than expected, it may indicate extra unmeasured anions. If it is lower than expected, the result may reflect low albumin, lab variation, or another less common cause.
The calculator is especially helpful when reviewing a electrolyte panel efficiently. For example, a low bicarbonate with normal chloride may point toward metabolic acidosis, while a low bicarbonate with a markedly elevated anion gap suggests a high gap acidosis.
It is important to remember that the calculator is only one step in clinical reasoning. It supports, but does not replace, a full assessment of symptoms, history, medications, and the rest of the lab pattern.
Expected Anion Gap Ranges and What Influences Them
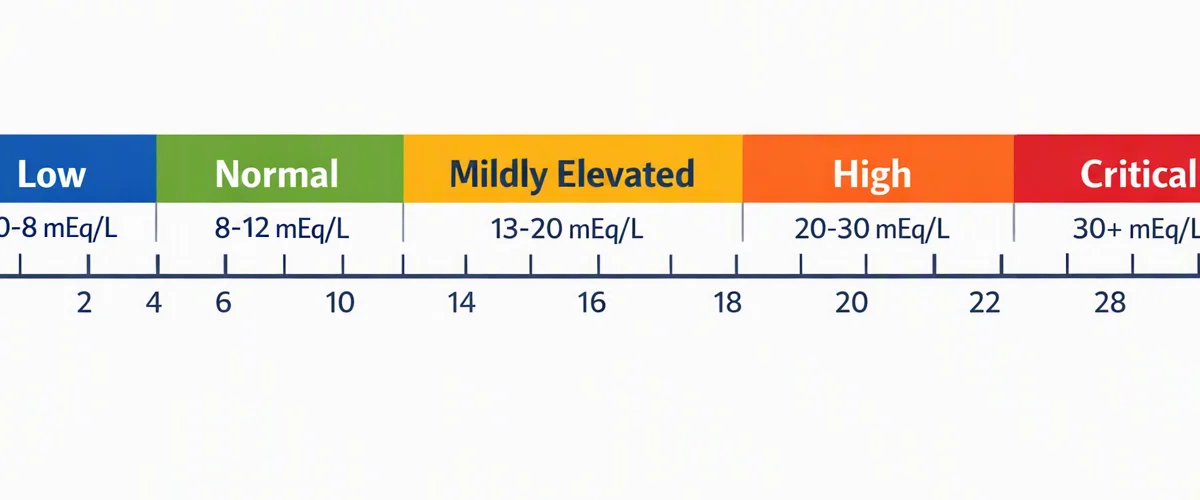
The expected range for the anion gap depends on the assay method and the lab’s normal interval or laboratory reference range. As different laboratories measure ions differently, a result that is “normal” in one setting may sit slightly outside the range used elsewhere.
That variability is one reason clinicians should always interpret the number in context rather than relying on a single cutoff. The lab’s stated normal range is the most useful guide for that specific result.
Albumin has a major effect on the anion gap because it is a negatively charged protein and contributes substantially to the pool of unmeasured anions. When albumin is low, the anion gap may appear falsely reduced even if an acid-base problem is present. This is where albumin adjustment becomes important.
An corrected-for-albumin or anion gap corrected for albumin estimate adjusts for low albumin so the result better reflects the true acid-base picture. In practical terms, if albumin is low, the corrected value may reveal a hidden elevation that would otherwise be missed. This helps reduce the risk of a false low anion gap.
Correcting for albumin is especially helpful when the patient has illness, inflammation, malnutrition, anion gap clinical significance liver disease, or fluid overload—situations where albumin may be below the usual range. In those cases, the raw result may not fully represent the patient’s actual acid-base status.
High Anion Gap Metabolic Acidosis Causes
A elevated anion gap is frequently associated with acidosis. This happens when acids build up in the blood and increase the amount of unmeasured anions. The bicarbonate level often falls because it is being utilized to buffer acid, and the anion gap goes up as a result.
Typical causes of elevated anion gap include:
- Lactic acidosis, which can occur when tissues are not well perfused or under marked metabolic strain Ketone-related acidosis, including diabetic or alcoholic forms Kidney failure, where the kidneys cannot eliminate acid effectively Exposure to certain toxins or drugs that create or retain acids
Lactic acidosis is a common cause of elevated gap results and frequently signals tissue hypoxia, sepsis, or other conditions that reduce oxygen delivery or utilization. Ketone-related acidosis often appears with increased ketones Click for more info and may be seen in diabetes, prolonged fasting, or heavy alcohol use. Renal failure contributes by reducing acid excretion and allowing acid metabolites to build up.
When the calculator returns a higher number, the next step is not just to label it abnormal. The key is to tie it to the patient’s overall clinical picture. For example, a low bicarbonate with a high anion gap is consistent with a high anion gap acidosis pattern, but the exact cause still requires focused evaluation.
In many cases, the anion gap is a useful starting point for a organized workup. Depending on the context, that may include lactate, ketones, creatinine, toxicology testing, and a blood gas to assess pH and compensation.
Low Anion Gap Causes and Clinical Relevance
A low anion gap is not as common than a high one, but it can be medically significant. The most frequent explanation is hypoalbuminemia, since albumin is a primary unmeasured anion. When albumin drops, the measured gap may decline even if the patient’s acid-base status is still unchanged.
Additional notable causes include multiple myeloma, lithium exposure, and paraproteinemia. These conditions can lower the calculated gap by introducing positively charged proteins or cations into the system, altering the balance of measurable ions.
Multiple myeloma and other paraproteinemia states can produce abnormal proteins that influence the result. This is why an unexpectedly low number should not be dismissed automatically. It can be a clue to a larger diagnostic process, especially if the patient also has anemia, kidney dysfunction, bone pain, or elevated total protein.
Lithium is a further notable cause because it is a cation that can affect the calculation. In the appropriate clinical setting, a low anion gap may provide an initial warning sign of lithium effect or toxicity.
As with a high result, a low value requires context. A low gap may be due to true disease, but it can also reflect a measurement issue or a misleading result from low albumin. Correcting for albumin and reviewing the full chemistry panel improves interpretation.
Interpreting Results for a Metabolic Panel
Effective metabolic panel interpretation begins with the overall picture, not the value alone. The anion gap should be reviewed alongside acid-base levels, sodium, chloride, bicarbonate, and the patient’s clinical status. A complete interpretation often reveals whether the problem is an electrolyte disturbance, an acid accumulation state, or a combination of both.
For instance, a low bicarbonate with elevated chloride may indicate a normal-gap acidosis with a chloride change. In that scenario, the body may be exchanging bicarbonate loss for chloride gain, keeping the anion gap within range even though acidosis is present. By contrast, low bicarbonate with a high anion gap points more toward acid accumulation from causes such as lactic acidosis, ketoacidosis, or renal failure.
The shift in chloride is important because chloride often rises as bicarbonate falls in certain forms of acidosis. That means a patient can have clear acid-base disruption even when the anion gap is not elevated. This is why the calculator should be used as part of a broader review of the entire electrolyte profile.
One practical approach is to interpret results in this order:
- Assess sodium, chloride, and bicarbonate for clear abnormalities Use the Anion Gap Calculator to detect a high or low pattern Assess whether albumin may require correction Compare the pattern with likely causes and symptoms Decide whether additional testing, including a blood gas, is needed
This method boosts the chance of identifying the correct acid-base problem and makes the result more useful than a standalone calculation. The anion gap is best viewed as a practical bridge between raw lab results and a diagnosis that explains what is happening physiologically.
Limitations, Common issues, and When to Recheck
Despite this a correctly used calculator has limitations. One important issue is laboratory error. A specimen problem, sample contamination, or analyzer issue can produce a misleading value. When the number does not fit the clinical picture, repeat testing is often the next next step.
Another pitfall is failure to account for hidden anions or protein-related effects. If albumin is low, the raw number may underestimate the severity of the underlying disturbance. If a patient has abnormal proteins or unusual cation exposure, the result may be shifted in the opposite direction.
A blood gas can be useful when the chemistry panel and symptoms do not align. It provides pH and respiratory compensation data, which can clarify whether the issue is truly metabolic, respiratory, or mixed. In patients with severe illness, the blood gas may also help confirm the urgency of the finding.
Recheck the result when:
- The number is inconsistent with the patient’s condition The specimen may have been handled poorly Albumin is not normal and correction has not been applied There is suspicion for a hidden acid-base problem Therapy has begun and response needs confirmation
In short, the calculator is useful, but it should not be treated as the final answer. A careful recheck can prevent misclassification and help distinguish a true abnormality from a transient or artifactual finding.
FAQ
What is an Anion Gap Calculator used for?
An Anion Gap Calculator is used to help interpret a metabolic panel by estimating the difference between measured electrolytes and identifying possible acid-base abnormalities. It is especially helpful for spotting a increased anion gap or reduced anion gap pattern and for guiding next-step clinical reasoning.
How do you calculate the anion gap from a metabolic panel?
The standard calculation for the anion gap is sodium - (chloride + bicarbonate). This calculation uses values from a standard metabolic panel or full metabolic panel. Many clinicians use a calculator to make this faster and reduce arithmetic errors.
What’s a normal anion gap range?
The normal reference range varies by laboratory because different analyzers and testing methods can alter the result. For that reason you should use the lab’s stated normal range or lab reference range rather than choosing one universal cutoff.
Why can the anion gap be high or low?
A high anion gap often suggests acidosis from causes such as lactic acidosis, ketoacidosis, or kidney failure. A decreased anion gap is often linked to low albumin, but it can also occur with myeloma, lithium therapy, or paraproteinemia.
Do you need albumin correction when interpreting the anion gap?
Yes, it should, when albumin is low, correction for albumin can improve interpretation and show a more accurate albumin-corrected anion gap. This is significant because hypoalbuminemia can make the gap look lower than it really is, leading to a spuriously low anion gap and a missed diagnostic clue.