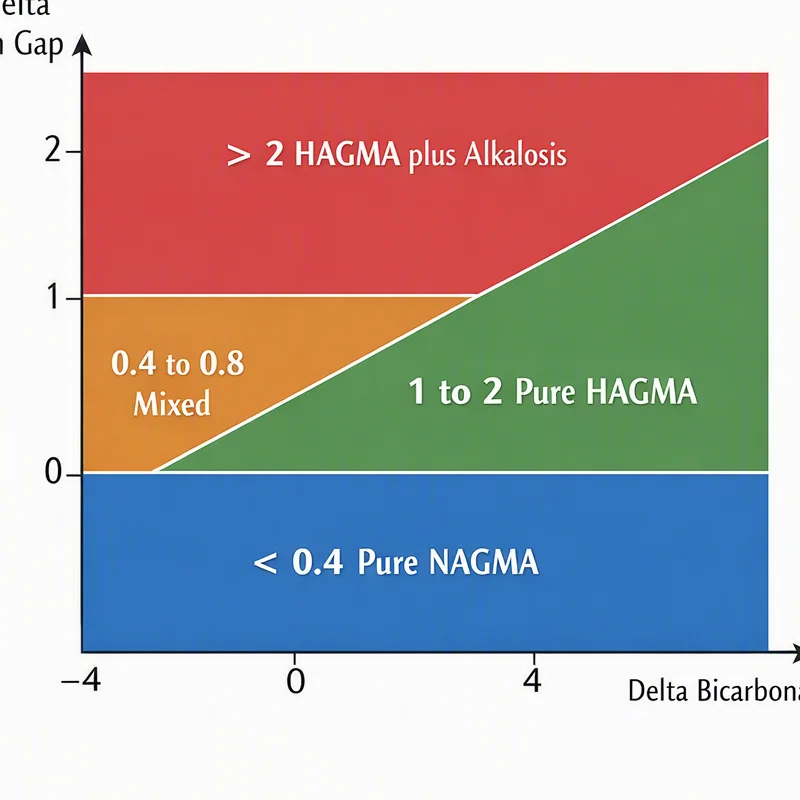
What the Anion Gap Shows
The anion gap is a practical way to measure acid-base balance by comparing the main positive and anionic components found in serum electrolytes. It enables clinicians identify hidden changes in the body’s chemistry that may not be obvious from a basic electrolyte review alone.
At its core, the anion gap shows the variation between routinely measured cations and anions in a electrolyte panel. Because not every charged particle is directly measured, the result gives an indirect estimate of unmeasured anions. This makes it a useful marker in the diagnostic evaluation of an acid-base disorder, especially when metabolic acidosis is suspected.
An elevated or reduced gap does not diagnose a condition by itself. Instead, it serves as a signal that can guide laboratory interpretation, prompt further testing, and support a broader review of serum chemistry and clinical findings. In practice, an anion gap calculator is a calculation tool that helps summarize these measured values rapidly and reliably.
How an Anion Gap Calculator Works
An anion gap calculator applies the primary measured electrolytes from a blood test to estimate the gap between positively charged ions and anions. Typical inputs include sodium, chloride, and bicarbonate. These results are generally included in routine serum chemistry results.
The most common version of the calculation matches sodium concentration with chloride concentration and bicarbonate level. Because sodium is the dominant measured cation and chloride and bicarbonate are key measured anions, the formula helps reveal shifts in electrolyte imbalance that may point to a metabolic problem.
This calculation is especially helpful in clinical decision support because it provides a fast snapshot of anion gap interpretation. A clinician can use it to determine whether a patient’s symptoms and lab values fit a metabolic disturbance such as acidosis, whether the pattern suggests extra unmeasured anions, or whether the result is likely within the lab reference range.
In numerous cases, the calculator is applied directly to the numbers from the lab report. That offers a straightforward way to interpret measured values without repeating the same equation each time.
Recorded Electrolytes Essential for Accurate Calculation
When calculating the anion gap correctly, you need the appropriate serum electrolytes from the identical blood draw when feasible. The usual inputs are serum sodium, serum chloride, and serum bicarbonate. These values come from the electrolyte panel and are essential for reliable laboratory interpretation.
Consistency matters because the calculation assumes the numbers reflect the same exact physiologic moment. If one result is outdated, drawn from a different sample, or affected by a testing issue, the gap may not accurately represent the patient’s current acid-base balance.
Besides the core values, clinicians often review related findings from the broader electrolyte panel. For example, an abnormal bicarbonate level may indicate buffering changes, while a shifted chloride concentration may help clarify whether the pattern looks like a normal anion gap issue or a high anion gap process.
Because the result depends on measured electrolytes, even small changes can affect the final number. This is why careful review of the source lab values is an important step before drawing conclusions.
Step-by-Step Anion Gap Formula
The usual anion gap formula is easy to follow:
Na minus Cl minus HCO3
In this formula, Na represents sodium, Cl represents chloride, and HCO3 indicates bicarbonate. Some forms of the formula also include potassium, but the most widely used approach in routine practice is the one above. It is favored because it is easy, fast, and practical for everyday anion gap interpretation.
To work with the formula, start with the sodium concentration, then take away the chloride concentration, and deduct the bicarbonate level. The result is the anion gap. An Anion Gap Calculator performs this instantly, reducing the chance of arithmetic mistakes and supporting efficient review of measured values.
The resulting number is then compared with the normal range or reference range provided by the laboratory. Different laboratories may use slightly different cutoffs depending on methodology and reporting standards, so it is best to interpret the result in the context of the specific lab reference range attached to the report.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the formula yields an anion gap of 14. Whether that is considered normal depends on the lab’s established reference range and the overall clinical picture.
Standard, Increased, and Low Anion Gap Results
A value within the expected reference range is often described as a normal anion gap. That does not automatically mean everything is normal, but it suggests there is no obvious rise in unmeasured anions based on the available results.
A high anion gap suggests an surplus of unmeasured acids or anions. This finding is commonly associated with metabolic acidosis and often prompts a deeper evaluation for underlying reasons. In this setting, the anion gap becomes a key part of anion gap interpretation and helps sharpen the differential diagnosis.
A reduced anion gap is rarer but can still be clinically relevant. It may reflect changes in protein levels, analytical errors, or shifts in measured electrolytes. Because low values can be ignored, careful review is important before assuming the result is insignificant.
Assessing these categories requires attention to the lab reference range. A value that seems abnormal in one context may be normal in another if the laboratory uses a different method or cutoff. That is why the reported reference range should consistently be checked before classifying the result.
Ultimately, the result is not interpreted in isolation. It should be paired with symptoms, the overall electrolyte panel, and the broader clinical question that led to the test.
Typical Causes of an Abnormal Anion Gap
An unexpected result frequently points toward a clear metabolic imbalance. One of the key causes of a high anion gap is metabolic acidosis, where acids accumulate or buffering is impaired. Common examples include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis can arise when tissues are underperfused, oxygen delivery is limited, or metabolism is further stressed. In these situations, lactic acid increases, and the anion gap may rise because of additional unmeasured acids.
Ketoacidosis is a further classic cause of high anion gap findings. When the body produces excess ketones, these acids add to the gap and may be seen with diabetes, starvation, or other states of reduced carbohydrate availability.
Renal failure can also increase the gap because the kidneys are less able to clear acid loads effectively. As acids accumulate, the result may shift away from the normal anion gap and toward a high gap pattern.
On the other end, a low anion gap may appear when albumin is reduced, when there is a testing artifact, or when unusual ions affect the calculation. Because the pattern is uncommon, it should be reviewed closely with the rest of the serum electrolytes and the patient’s clinical picture.
Adjusting the Anion Gap for Albumin
Albumin is a important unmeasured anion in blood, so it has a strong effect on the calculated gap. When hypoalbuminemia is present, the measured result may appear lower than expected even if extra acids are present. That is why albumin correction is an key part of modern anion gap interpretation.
The corrected anion gap adjusts the result to account for low albumin. This matters because a patient with hypoalbuminemia may have a misleadingly normal or only mildly elevated gap despite a significant acid-base problem. Without correction, the underlying disorder could be missed.
Using the corrected anion gap helps enhance diagnostic accuracy, especially in patients with chronic illness, poor nutrition, inflammation, or other conditions associated with low protein levels. In these cases, the calculator should be used as part of a more complete review rather than as a stand-alone number.
Albumin correction is not always required, but it is often helpful when the measured result and the clinical picture do not match. When the gap seems unexpectedly low or borderline, checking the albumin level can aid interpretation and reveal hidden metabolic changes.
How to Interpret Results in Medical Context
The best way to interpret an anion gap calculator is in combination with the rest of the clinical picture. A single value can point to a direction, but an accurate diagnosis depends on symptoms, history, and other labs. In practice, interpretation often includes the arterial blood gas, the electrolyte panel, and other measures of organ function.
The arterial blood gas can show whether the patient has acidemia or alkalemia and whether respiratory compensation is present. When paired with the electrolyte panel, it helps define the specific acid-base disorder. This is especially important if the bicarbonate is low or if the patient has signs of shock, dehydration, toxin exposure, or kidney dysfunction.
A high anion gap with low bicarbonate often suggests the presence of metabolic acidosis. But not all metabolic acidosis is the same. Some cases are related to lactic acid, some to ketones, and others to impaired renal clearance. The pattern of serum electrolytes can help pinpoint which mechanism is most plausible.
A normal value does not always exclude disease. For example, mixed disorders can mask abnormalities, and a low albumin level can blunt the expected rise. That is why anion gap interpretation should be paired with clinical examination, diagnosis-focused testing, and careful review of all available measured values.
Limitations and Frequent Calculation Errors
Even though the anion gap is easy to calculate, several issues can affect calculation accuracy. One of the most common is measurement error. If the source lab result is wrong, contaminated, or collected improperly, the final number may not reflect the patient’s true status.
Lab variation is another important factor. Different instruments and reporting methods can produce slightly different values for sodium, chloride, or bicarbonate. As a result, the same patient may have a different result depending on the laboratory, making the lab reference range essential for interpretation.
Another common problem is working with mismatched samples. If sodium was drawn at one time and chloride or bicarbonate at another, the value may be misleading. The best practice is to use a single, unified electrolyte panel whenever practical.
Readers should also avoid misjudging a borderline abnormal result without clinical context. A small shift may be due to routine variation rather than a true metabolic disturbance. Likewise, a clearly abnormal value should prompt review of the entire clinical situation rather than a reflex conclusion based on the calculator alone.
In short, the tool is only as good as the input. Careful review of serum electrolytes, attention to measurement error, and awareness of lab variation are key to dependable anion gap interpretation.
Frequently Asked Questions
What is a normal anion gap?
The anion gap normal range depends on the laboratory method and the reported reference range. In many settings, the value is considered normal when it falls within the lab’s stated cutoff. Because methods vary, the most accurate interpretation is the one that matches the specific lab reference range listed with the result.
How do you calculate the anion gap from measured electrolytes?
Use the standard anion gap formula: Na minus Cl minus HCO3. Enter the measured sodium, chloride, and bicarbonate values from the same electrolyte panel. An anion gap calculator makes this process faster and reduces the chance of arithmetic mistakes.
Why is albumin used to correct the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap appear falsely low. Albumin correction helps produce a more accurate corrected anion gap, especially in patients with hypoalbuminemia. This improves the detection of hidden acid-base abnormalities.
What causes a raised anion gap?
Typical high-gap causes include lactic acidosis, ketosis-related acidosis, and renal insufficiency. These conditions increase unmeasured acids or impair acid clearance, leading to acid-base acidosis and a elevated calculated gap.
Can a low anion gap be clinically significant?
Yes. A decreased anion gap can be medically important, especially when linked to decreased albumin, anion gap units comparison a testing issue, or other abnormalities in serum electrolytes. It should not be ignored, particularly if the result does not fit the rest of the acid-base balance picture.