What Is the Anion Gap?
The anion gap is a calculated value that helps assess acid-base status by comparing the main measured electrolytes in a blood sample. It is often obtained from a serum chemistry panel or other serum electrolytes results, using the relationship between sodium, chloride, and bicarbonate. Clinically, it is used to identify whether there are unmeasured anions contributing to an anion deficit and an underlying acid-base disorder.
In simple terms, the anion gap is a diagnostic tool that estimates the difference between positively charged and negatively charged particles in the blood. That difference reflects electrolyte balance and can point to a metabolic disturbance that is not obvious from the individual values alone. Because it is based on routine blood chemistry, it is often used as a screening test during patient assessment.
Most modern labs provide the ingredients needed for the calculation as a standard laboratory result. Even though the concept sounds abstract, the practical use is straightforward: if the gap is elevated, clinicians think about causes of metabolic acidosis, especially high anion gap metabolic acidosis.
Anion Gap Formula Without Potassium
The standardly used calculation method without K is given by:
Anion gap = sodium - (chloride + bicarbonate)
This method uses serum sodium, chloride level, and bicarbonate value values from the lab. When you use an Anion Gap Calculator, this is typically the default method because it is easier and aligns with common medical practice.
All values are typically reported in mEq/L. The formula takes away the total of chloride and bicarbonate from sodium. Since sodium is the primary measured cation in the panel, and chloride plus bicarbonate are the primary measured anions, the result approximates the space left by negative charge from unmeasured substances.
Even though some older formulas also included potassium, many clinicians omit it because the contribution is small and generally does not alter the practical interpretation in practice. A simplified formula makes the calculation more convenient without sacrificing much utility in routine use.
If you check the result manually, make sure the units are consistent and that the numbers come from the same laboratory values set. An error in units or transcription can change the result significantly.
Stepwise Math Illustration
Here is a straightforward worked example based on typical laboratory values:
- Na = 140 mEq/L Cl = 102 mEq/L HCO3 = 24 mEq/L
Using the formula:
Anion gap = 140 - (102 + 24)
Start by combining chloride and bicarbonate:
102 + 24 = 126
Next take away from sodium:
140 - 126 = 14
This value is 14 mEq/L. According to the laboratory expected range, this may be viewed as normal or mildly elevated. This is why the result must always be interpreted in its clinical context rather than as a stand-alone number.
Relying on an anion gap calculator can reduce arithmetic mistakes, but the manual method is easy to check. The key is to remember the exact method and to use current lab values rather than outdated results. When values change rapidly, the gap can shift along with the patient’s blood acid-base status.
Typical Values and Meaning
A normal anion gap depends on the laboratory normal range, the measurement method, and whether potassium is included. In many cases, a typical non-potassium result is roughly in the low teens, but the exact normal interval changes from one lab to another. Always compare the number with the lab’s stated range instead of relying on a universal cutoff.
A high anion gap suggests extra unmeasured acids in the blood. This pattern is commonly associated with metabolic acidosis, especially elevated anion gap metabolic acidosis. The finding can help focus the differential diagnosis, but it does not identify the cause by itself.
One important factor is serum albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear lower than expected. In those cases, clinicians may use an corrected anion gap to get a more precise corrected value. This is especially useful when evaluating a suspected acid-base disorder in patients with hypoalbuminemia.
Interpretation should also distinguish high-gap from non-anion gap metabolic acidosis. A normal gap does not rule out acidosis; it may indicate bicarbonate loss with a compensatory rise in chloride, as seen in normal-gap patterns. That is why the number should always be interpreted alongside the full chemistry panel and the broader clinical picture.
How come Potassium Is Often Excluded
Potassium is often excluded because its concentration is far lower than sodium, and the difference usually has little impact on everyday clinical practice. The simplified formula improves consistency and accelerates use in busy settings. Many forms of laboratory reporting also leave out potassium for this reason.
From a practical standpoint, leaving potassium out makes the calculation simpler to recall and reduces the chance of error. The change in result is usually small enough that it does not change the general conclusion, especially when the goal is basic screening rather than advanced analysis.
That said, the omitted-potassium method is not a different concept. It is the same physiologic idea, just a simplified approach built into many calculators and lab systems. If an older source includes potassium, the resulting number will be a bit higher, but the overall assessment of acid-base status often stays similar.
In other words, the anion gap calculator commonly used in practice is based on the simplified formula because it is effective, consistent, and adequate for most patient assessment scenarios.
Origins of a High Anion Gap
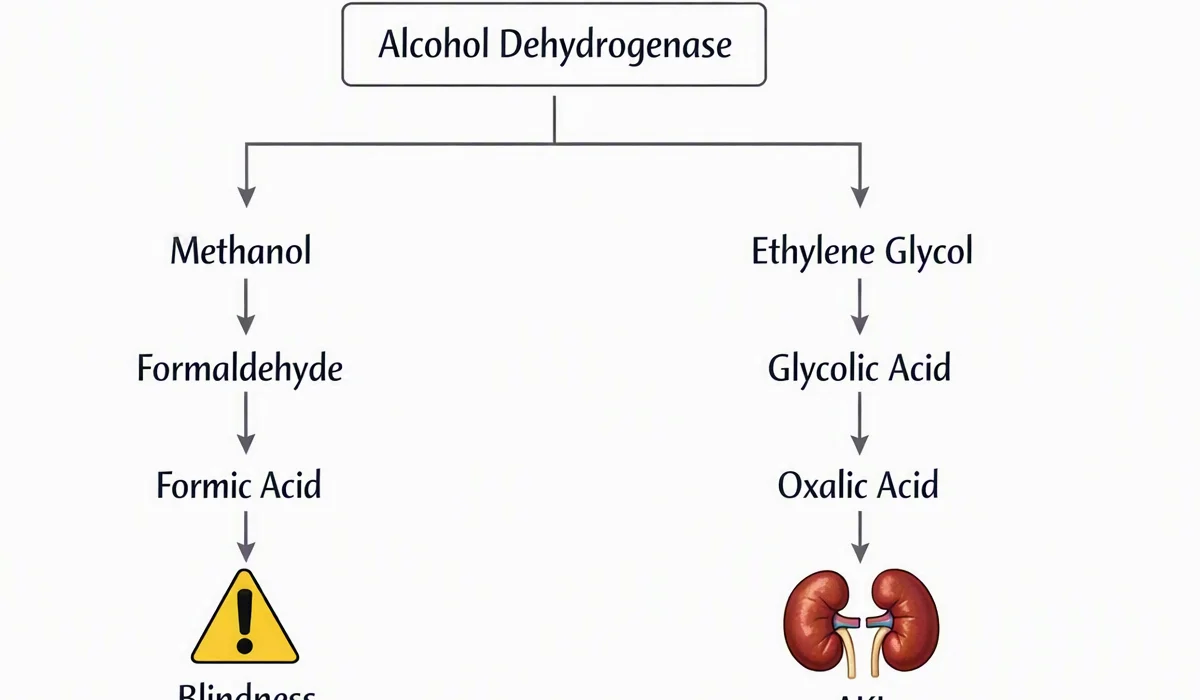
A elevated result indicates extra acid or undetected anions in the bloodstream. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. Each of these can elevate the gap for a separate reason, but all lead to an build-up in undetected acids.
Lactic acidosis occurs when lactate accumulates, often in contexts of inadequate perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis arises when ketones rise, such as in diabetes or prolonged fasting. Renal failure can reduce acid excretion, allowing acids to collect. Toxic ingestions may expose the body to substances that are metabolized into acids or that interfere with normal metabolism.
These causes are especially important when the anion gap is elevated together with signs of metabolic acidosis. A clinician may use the gap as a clue, then pair it with history, physical findings, and additional testing to find the underlying problem. The gap itself is a indicator, not a final diagnosis.
Because different disorders can produce the same pattern, the value should be considered part of a broader diagnostic framework. A patient with high-gap acidosis needs a targeted evaluation, and the anion gap calculator can help flag the issue early.
Limitations of the Anion Gap Calculator
An anion gap calculator is valuable, but it has significant drawbacks. The first is albumin adjustment. Since albumin is a primary contributor to the normal gap, low albumin can hide a medically important elevation. If not adjusted, the result may look inaccurately reassuring.
Also, the value varies with the testing facility’s reference range. Different methods, analyzers, and reporting practices can produce different values, so a finding that seems abnormal in one setting may be appropriate in another. That is why interpretation should always be tied to the particular laboratory’s reference interval.
Third, laboratory error may distort the outcome. Sample contamination, delayed processing, or recording mistakes can affect sodium, chloride, or bicarbonate values. Since the gap is computed from these values, even one inaccurate test result can lead to a incorrect conclusion.
In the end, the result is only a single part of the evaluation. It does not replace a complete clinical review, arterial or venous blood gas when needed, or checking for other causes of acid-base imbalance. If used well, it is a useful screening tool; on its own, it can be insufficient.
Frequently Asked Questions
How is calculated anion gap without potassium?
Use the formula the formula sodium - (chloride + bicarbonate). This remains typical basic formula and serves as the way most anion gap calculator resources use. Type in the lab values in mEq/L and subtract the sum of chloride and bicarbonate from sodium.
What is the formula for an anion gap calculator without potassium?
The equation is anion gap = sodium - (chloride + bicarbonate). It takes the key serum electrolytes from the lab panel and excludes potassium for simplicity. This remains the most widely used calculation formula in regular use.
What is a typical anion gap excluding potassium?
The normal values are based on the lab’s normal range and measurement method. Most laboratories consider a low-teens result normal when potassium is excluded, but you should always compare the number to the reported lab range on that specific lab result.
Why is potassium often left out of the anion gap calculation?
Potassium is usually excluded because it contributes albumin correction AG rationale relatively little to the overall result. Leaving it out creates a streamlined formula that fits common clinical practice and laboratory reporting standards without meaningfully changing everyday clinical interpretation.
What does a high anion gap mean clinically?
A high result suggests more unmeasured acid buildup and is often associated with metabolic acidosis, especially anion gap metabolic acidosis. Common causes include lactate buildup, ketosis-related acidosis, renal impairment, and poisoning. The value supports evaluation, but the cause requires further assessment.