What the anion gap measures
The anion gap is a derived value that helps clinicians assess whether there are extra acids in the blood that are not directly measured on routine electrolytes. It is obtained from the major measured ions in a basic serum chemistry panel and used as a diagnostic clue in evaluating acid-base balance.
Although the name suggests a true “gap,” it does not represent missing space. Instead, it reflects the difference between measured cations and measured anions, which indirectly suggests the presence of unmeasured anions. These can include acids and other ions that collect during illness.
In practical terms, the anion gap helps narrow down causes of metabolic acidosis. A higher-than-expected value can indicate acid accumulation, while a normal value with acidosis can point to a different process. That is why the calculation is commonly used alongside the full clinical context, not in isolation.
Anion gap formula and calculator inputs
A anion gap calculator relies on a simple formula that uses sodium, chloride, and bicarbonate. A common equation is:
Anion gap = sodium − (chloride + bicarbonate)
Some formulas also use potassium, but it is often left out in routine calculations because its contribution is small. With potassium included, the formula becomes:
Anion gap = (sodium + potassium) − (chloride + bicarbonate)
In most bedside and laboratory interpretations, the first formula is the one used. The key inputs are the electrolyte values from the patient’s blood test. Careful measurement matters because even small shifts in any of these values can change the result.
In clinical use, the calculator estimates whether there are extra unmeasured ions or unmeasured anions present. That is why, the anion gap is often paired with other data, such as pH, bicarbonate level, and sometimes lactate or ketones, depending on the suspected cause.
Step-by-step method to estimate anion gap
If you want to calculate the anion gap manually from an electrolyte panel, the method is straightforward. Take the values from the same blood draw whenever possible, since mismatched results can cause confusion.
Step 1: Find the serum sodium value.
Step 2: Identify the serum chloride value.
Step 3: Find the serum bicarbonate value.
Step 4: Add chloride and bicarbonate together.
Step 5: Deduct that sum from sodium.
As an example: If serum sodium is 140, serum chloride is 102, and serum bicarbonate is 24, then:
140 − (102 + 24) = 140 − 126 = 14
That calculated anion gap would be 14. Whether that is normal depends on the lab’s reference range and whether albumin is low. The same lab result may be viewed differently depending on the patient’s overall condition https://anion-gap-widget910.nexorafield.com/posts/anion-gap-calculator-for-kidney-function-assessment and whether there is an acid-base disorder.
Using an anion gap calculator can reduce arithmetic errors, especially when reviewing multiple electrolyte values quickly. However, understanding the formula is important because interpretation depends on not just the number alone.
Standard range, albumin correction, and clinical interpretation
The normal anion gap depends on the laboratory method and the instrument used, so the best first step is to confirm the local reference range. Many labs use a relatively tight range, and small differences in measurement can affect whether a result is labeled low, normal, or high.
Albumin has an important role because it is a anionic protein and one of the main unmeasured anions. When albumin is low, the anion gap may appear falsely normal or only mildly elevated even if significant acid is present. This is where albumin correction becomes important.
A commonly used approach is to raise the anion gap upward when albumin is below normal. The exact formula varies by institution, but the purpose is the same: to estimate the corrected anion gap more accurately by accounting for reduced albumin.
For example, if a patient has a low albumin level, a borderline anion gap may actually reflect more substantial acid accumulation than the raw number suggests. That can change the interpretation of the lab result and affect further steps in evaluation.
It is also helpful to remember that a “normal” result does not automatically rule out an acid-base problem. The value must be interpreted alongside the pH, bicarbonate, and the rest of the serum chemistry profile. A careful read of the entire picture gives a much better estimate of what is happening physiologically.
High anion gap compared with expected anion gap metabolic acidosis
Metabolic acidosis happens when acid collects or bicarbonate is depleted. The anion gap helps separate this into two broad types: high anion gap metabolic acidosis and normal anion gap metabolic acidosis.

In high anion gap metabolic acidosis, the body has added acids that generate extra unmeasured anions. Bicarbonate drops because it neutralizes those acids, and the anion gap widens because the additional negative charges are not measured directly. Common examples include lactic acidosis and ketoacidosis.
In normal anion gap metabolic acidosis, bicarbonate is removed or exchanged for chloride, but the anion gap stays within the expected range. This pattern is sometimes called hyperchloremic acidosis because chloride rises as bicarbonate falls.
Lactate is a especially important clue in high-gap states. A elevating lactate level may suggest tissue hypoperfusion, sepsis, or another cause of increased acid production. The anion gap does not replace lactate testing, but it can encourage the clinician to look for it sooner.
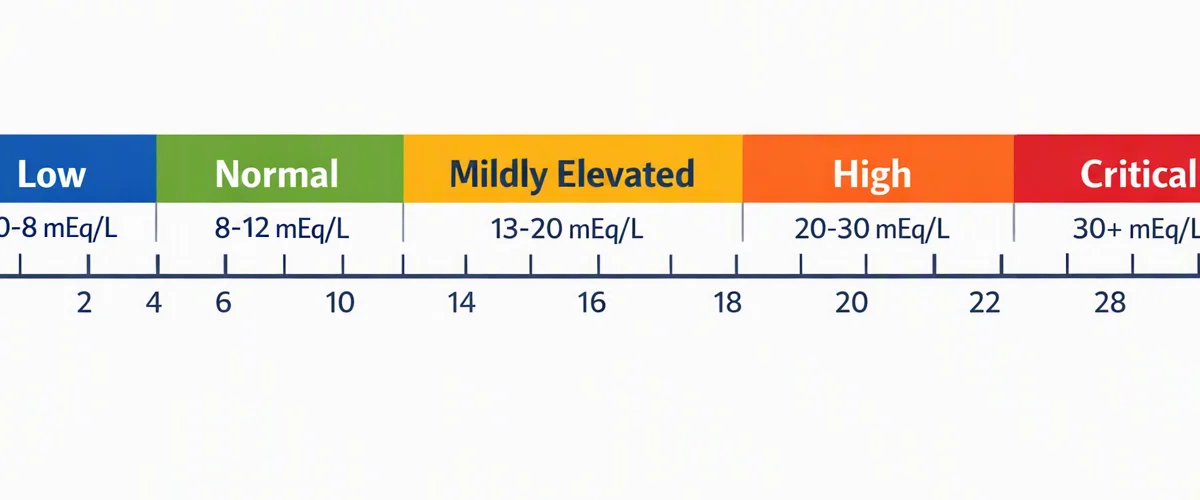
The distinction matters because the differential diagnosis varies. A high gap points toward retained acids or toxins, while a normal gap with acidosis points more toward bicarbonate loss or renal handling problems.
Frequent causes of an abnormal anion gap
A number of conditions can cause an abnormal anion gap, and the result often gives the first hint about the source of the problem. The main high-gap causes include ketoacidosis, renal failure, and toxin exposure.
Ketoacidosis develops when ketones accumulate, often in uncontrolled diabetes, starvation, or prolonged poor intake. These ketones act as unmeasured anions and can greatly increase the anion gap.
Renal failure can also elevate the gap because the kidneys cannot clear acid effectively. As acids build up, bicarbonate falls and the balance shifts toward a elevated gap.
Toxins are another important category. Salicylates can cause complex acid-base disturbances and may elevate the anion gap. Toxic alcohols, such as methanol and ethylene glycol, are typical causes of severe high-gap metabolic acidosis and should always be considered when the clinical picture fits.
Other causes may include lactic acidosis, but the list above covers several of the most important and urgent possibilities. The key point is that an abnormal result is a signal to investigate the source of the acid-base disorder, not a diagnosis by itself.
Constraints and usual calculation mistakes
Although a proper formula can produce a deceptive answer if the lab values are not understood carefully. One common problem is using values from different sample times or different collection methods. Because electrolytes can change quickly, the timing of the data matters.
Measurement error is one more limitation. Small inaccuracies in sodium, chloride, or bicarbonate can shift the result enough to move it across the normal range. This is one reason the anion gap should always be reviewed in the context of the overall presentation.
One more frequent mistake is ignoring potassium when a particular calculator includes it, or adding it when the intended formula does not. Since calculators may vary, it is important to know which formula is being used before comparing results.
Serum albumin is also commonly overlooked. If albumin is low, the raw anion gap may underestimate the degree of acid accumulation. That is why albumin correction can be so useful.
In the end, do not overinterpret a single abnormal value. The true meaning depends on the clinical context, the symptoms, the blood gas, and the rest of the serum chemistry profile. The anion gap is best viewed as one piece of the diagnostic puzzle.
When to use an anion gap calculator
An anion gap calculator is especially helpful when you are reviewing electrolyte abnormalities and need a fast way to look for acid-base problems. It can help show whether the pattern fits a high-gap state or suggests a normal-gap process instead.
It is particularly useful when assessing suspected acid-base disorders. If bicarbonate is low, the calculator can help determine whether the issue is likely due to added acids or to bicarbonate loss. That makes it a practical tool for quick bedside reasoning.
An arterial blood gas adds important information about pH and ventilation, but it does not replace the anion gap. Using both together gives a more complete estimate of the disorder and can reveal mixed conditions that might otherwise be missed.
For clinical decision making, the calculator is highest value when it is used as part of a broader review rather than as a stand-alone number. If the result is abnormal, the next step is to ask what type of acid-base disorder is present and what source is driving it.
Frequently asked questions about determining anion gap
How do you calculate anion gap from electrolyte values?
Use the formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium − (chloride + bicarbonate). You can calculate it manually from the electrolyte values on a serum chemistry panel or use an anion gap calculator for efficiency and consistency.
What formula is used in an anion gap calculator?
Most calculators use anion gap = sodium − (chloride + bicarbonate). Some also include potassium, but many routine calculations do not. The calculator should always show which formula is being used so the result can be interpreted correctly.
Should albumin be included when interpreting the anion gap?
Yes. Albumin should be considered because low albumin can make the anion gap appear lower than it really is. An albumin-adjusted anion gap or albumin correction can improve the interpretation, especially when evaluating metabolic acidosis.
What does a high anion gap mean?
A high anion gap usually indicates more acids or additional unmeasured anions in the blood. Typical causes include lactic acidosis, ketoacidosis, renal failure, salicylates, and toxic alcohols. What it means depends on the full clinical context.
What are common causes of a normal anion gap with acidosis?
Common causes of normal anion gap metabolic acidosis include gastrointestinal bicarbonate loss, renal tubular acid-handling problems, and other conditions that lower bicarbonate without creating a large buildup of unmeasured acids. Reviewing the electrolyte pattern, blood gas, and clinical picture helps narrow the diagnosis.
When applied effectively, the anion gap is a practical estimate that turns routine electrolyte values into meaningful diagnostic information. It helps clinicians identify metabolic acidosis, differentiate high-gap from normal-gap patterns, and decide what to check next.
