Yes, dehydration can impact the anion gap, but usually indirectly rather than directly. The main issue is that fluid loss can change blood volume and cause concentration variations in lab values, which may lead to the result seem different without necessarily meaning there is a dangerous metabolic problem. An Anion Gap Calculator can help you estimate the number, but clinical interpretation depends on the full picture, including the electrolyte panel, serum bicarbonate, albumin, and symptoms.
This difference matters. A changed result may reflect simple hemoconcentration from fluid loss, or it may point to a genuine acid-base issue such as metabolic acidosis. Knowing the difference helps you know when the result is likely temporary and when it needs a deeper evaluation.
What’s the Anion Gap?
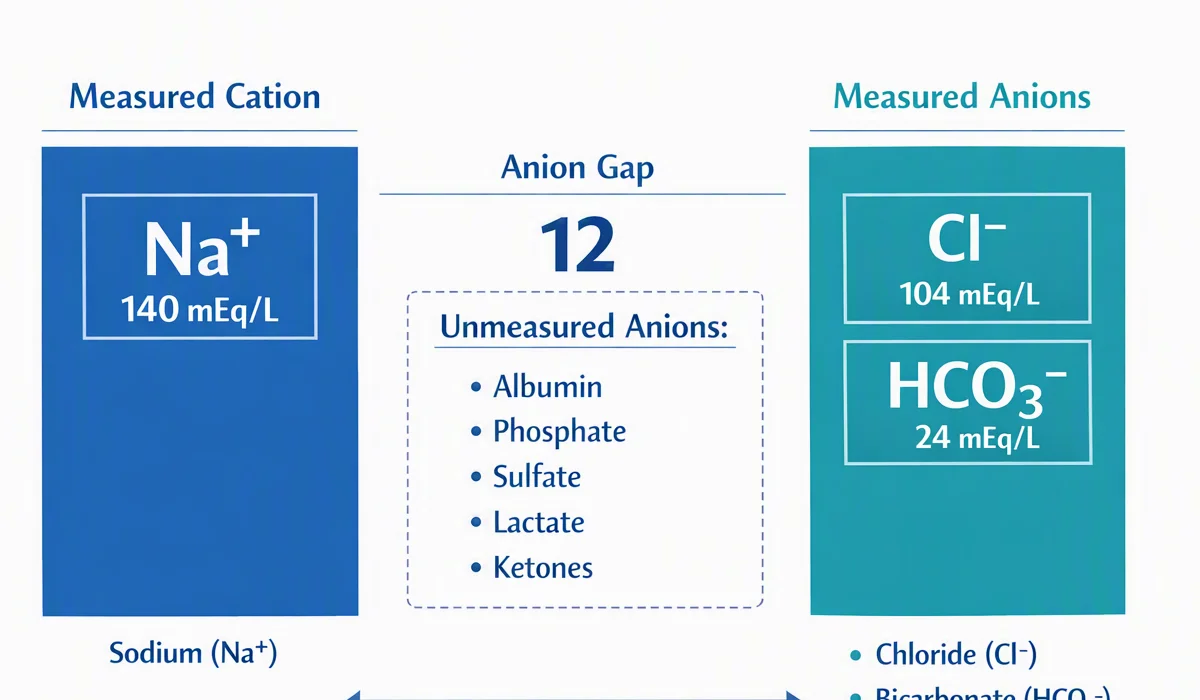
The anion gap is a calculated value used in blood chemistry to examine acid-base balance. It is not a measured value. Instead, it shows the gap between commonly measured ions, especially sodium and chloride, along with bicarbonate in many formulas. This makes it a useful diagnostic marker for certain kinds of metabolic disorder.
Simply put, the anion gap helps clinicians look for unmeasured ions in the blood. If the gap is above normal, it can suggest extra acids are present. If it is reduced, it may suggest low protein levels, lab issues, or less unmeasured positive ions than usual.
The specific reference range can differ depending on the lab and the method used. That is why clinical interpretation should always use the result from the same laboratory or a trusted medical testing source rather than a fixed number.
The key components behind the calculation are part of routine serum electrolytes. Because these are commonly included in a basic metabolic panel or a broader electrolyte panel, the anion gap is often available even when it is not ordered as a separate test. That makes it a useful tool for assessing blood chemistry and spotting abnormal results.
How an Anion Gap Calculator Works
An anion gap calculator uses the numbers from a blood test to approximate the gap fast. Many calculators use sodium, chloride, and serum bicarbonate. Some formulas also adjust for albumin, because albumin is a key unmeasured anion and can strongly influence the result.
The usual logic is simple: the calculator performs an anion calculation by balancing the measured cations and anions in the sample. When bicarbonate is low, the gap often rises because bicarbonate is being consumed or lost while unmeasured acids accumulate. When albumin is low, the gap follow this link may look lower than expected even if the true acid-base state is more complex.
This is why a calculator is useful, but not sufficient. It provides a numerical estimate, not a diagnosis. The result must be interpreted alongside the electrolyte panel, the basic metabolic panel, and the patient’s overall condition. In plain terms, the calculator is best used as part of supportive assessment, not as a single answer.
Albumin deserves special attention. Because it carries negative charge, low albumin can reduce the measured gap. Numerous clinicians will consider a correction when hypoalbuminemia is present, since failing to account for it can hide a clinically important high anion gap.
Can Fluid loss Change the Anion Gap?
Lack of fluids can alter the anion gap, but the effect is often due to reduced body fluid and more concentrated blood rather than a direct shift in acid production. When blood volume falls, some blood components become more concentrated. That can skew laboratory results on a blood draw and make results look more abnormal than they would after rehydration.
In slight dehydration, the anion gap may not vary much at all. In more significant dehydration, especially when accompanied by vomiting, poor intake, or illness, the numbers can move enough to stand out. However, the key question is whether the change reflects simple electrolyte imbalance or a true metabolic problem.
Dehydration alone does not usually cause a major high anion gap. Instead, it may contribute to related problems that raise the gap, such as reduced kidney clearance, lactic acid buildup from poor perfusion, or ketone production if intake is very low. That is why a changed result should prompt the question: what is the root cause?
From a real-world standpoint, dehydration can also make an already abnormal result look worse. A person with underlying illness may have borderline blood chemistry, and fluid loss can intensify the apparent abnormality. This is where careful results interpretation matters most.
Why Lack of hydration Can Alter Lab Results
A key way dehydration impacts testing is through hemoconcentration. When plasma water is reduced, measured substances in the blood can become more concentrated. That can change lab values across the full panel, including sodium, chloride, bicarbonate, and other markers on a basic metabolic panel.
Another important factor is kidney function. The kidneys help regulate water, electrolytes, and acid-base status. If dehydration reduces kidney perfusion, the body may briefly retain waste products and alter serum chemistry. For this reason BUN and creatinine are often reviewed together. A higher BUN-to-creatinine pattern can suggest dehydration, though the overall context matters.
Dehydration can also be a clue that the body is under stress from illness, not just lacking water. As an example, vomiting, fever, diarrhea, or poor intake can lead to both fluid loss and metabolic changes. In those situations, the lab pattern may reflect more than simple dehydration, and the anion gap becomes one piece of a larger puzzle.
It can be useful to consider the result as part of an integrated review of blood chemistry. If BUN is elevated, creatinine is affected, and the anion gap is abnormal, the pattern may indicate dehydration-related strain on the kidneys or another process altogether. Here a clinician compares the numbers with symptoms and exam findings.
When a Raised Anion Gap Is More Concerning
A high anion gap is more alarming when it suggests acid buildup. That indicates acids are accumulating in the body more quickly than they can be removed or buffered. Dehydration may coexist with this condition, but it is almost never the only explanation when the gap is clearly elevated.
Common causes include lactate buildup, ketone-related acidosis, and poisons. Lactic acidosis can happen when tissues do not get enough oxygen or blood flow, which may occur in severe illness or substantial volume depletion. Ketoacidosis can occur with diabetes, prolonged fasting, alcohol use, or very low carbohydrate intake. Certain toxins and medications can also produce a harmful acid load.
These causes matter because they are genuine metabolic problems, not just concentration effects from dehydration. A person may be dehydrated and also have one of these conditions. In that case, the dehydration may worsen the issue, but the main concern is the root acid accumulation.
If the anion gap is high, the rest of the panel becomes important. Low blood bicarbonate, a changing chloride pattern, and other signs of salt imbalance can support the diagnosis. The most useful approach is not to focus on one number alone, but to ask whether the pattern fits a known cause of acid-base disturbance.
Reduced Anion Gap: Additional Possible Causes
A reduced anion gap is rarer than a raised one, and dehydration is generally not the primary cause. One major explanation is hypoalbuminemia, since albumin is a key negatively charged protein. If albumin is decreased, the calculated gap can decrease even if there is no major acid-base disorder.
Another possible cause is multiple myeloma or other conditions that elevate abnormal proteins in the blood. These proteins may behave as positive ions or otherwise alter the balance between measured and unmeasured particles. In such cases, the low gap can be a clue that more testing is needed.
Lab error is also a real issue. Because the anion gap is calculated from several measured values, a small mistake in one input can create a misleading result. Repeating the electrolyte panel or reviewing the sample handling may help if the number does not fit the clinical picture.
When a low result appears, clinicians often review the entire basic metabolic panel, the albumin level, and any signs of protein disorders or medication effects. As with a high result, the goal is to identify the actual cause rather than assuming the calculator result is the diagnosis.
Symptoms That Need Medical Attention
Some signs indicate that a changed anion gap may be part of a more severe illness. Confusion, rapid breathing, and vomiting can occur when the body is dealing with acid-base problems or severe dehydration. These symptoms deserve prompt attention, especially if they come on quickly or worsen.
Severe dehydration can lead to dizziness, weakness, dry mouth, very dark urine, fainting, and reduced urine output. If severe dehydration is paired with abnormal blood chemistry, the risk of kidney strain and metabolic complications increases. That is why symptom evaluation is as important as the number itself.
Prompt medical care may be needed when symptoms suggest worsening acid-base imbalance, poor circulation, or inability to keep fluids down. A clinician may order repeat medical testing to check the anion gap, serum bicarbonate, kidney markers, and other data points. The mix of symptoms and lab data guides the next step.
If you are using an anion gap calculator and the number is abnormal, do not rely on the calculator alone if you feel unwell. Symptoms can reveal a problem that the number only hints at. In that situation, timely medical evaluation is the safest choice.
Frequently Asked Questions About Dehydration and the Anion Gap
Can dehydration cause a high anion gap?
Dehydration can be associated with a high anion gap, but usually indirectly. Fluid loss can reduce blood volume, cause hemoconcentration, and contribute to kidney stress or poor tissue perfusion. Such changes can raise the gap if they lead to metabolic acidosis, lactic acidosis, or ketone buildup. Dehydration alone is not usually the full explanation.
Can dehydration cause a low anion gap?
Dehydration is not a common cause of a low anion gap. Low results are more often linked to hypoalbuminemia, multiple myeloma, lab error, or other shifts involving positive ions. If dehydration is present, it may affect lab values, but a low gap usually calls for a broader review.
What is the normal anion gap range?
The anion gap range varies by the laboratory, the instrument, and whether albumin is considered. Many labs use a tight reference range, but there is no single universal value. For most accurate clinical interpretation, match your result with the range printed on the report and interpret it in the context of the electrolyte panel and bicarbonate level.
Should I drink water before repeating an electrolyte test?
If dehydration may have affected the result, moderate water intake may help restore fluid loss balance, but do not assume hydration alone will explain the abnormality. A repeat chemistry panel or basic metabolic panel should be done according to the instructions from your clinician. If you have vomiting, confusion, or trouble keeping fluids down, seek medical care rather than trying to self-correct the numbers.
When should a changed anion gap be evaluated by a doctor?
A changed result should be evaluated when it is clearly outside the expected expected range, when it comes with symptoms like mental confusion, fast breathing, or vomiting, or when there are signs of severe dehydration or renal impairment. A clinician may review blood urea nitrogen, serum creatinine, serum albumin, and the full blood chemistry to identify the underlying cause and decide whether more testing is needed.