What the Anion Gap Is Measured
The anion gap is a calculated value that supports read an electrolyte panel and recognize certain acid-base disorder patterns. It contrasts the main positively charged and negative particles in serum electrolytes, especially sodium, chloride, and bicarbonate. Because routine chemistry tests do not measure every charged particle in the blood, the anion gap approximates the difference between measured cations and measured anions.
In clinical terms, a low, normal, or elevated anion gap can be a useful diagnostic clue during blood test interpretation. A high value often raises concern for metabolic acidosis, while a low anion gap indicates a different set of possibilities such as hypoalbuminemia, laboratory issues, or excess unmeasured positive ions. The result should always be read together with the rest of the serum chemistry panel and the patient’s symptoms.
The exact formula used for anion gap calculation may differ by laboratory, but it usually relies on sodium, chloride, and bicarbonate. Because these components are part of standard chemistry testing, the anion gap is not a direct measurement. It is a derived number that reflects acid-base balance and broader electrolyte imbalance patterns.
In What Way an Anion Gap Calculator Operates
An Anion Gap Calculator employs the formula chosen by a given laboratory to estimate the gap from sodium, chloride, and bicarbonate values. Numerous calculators also offer albumin correction, which is important because albumin is a principal unmeasured anion in blood. When albumin is low, the displayed anion gap may be artificially lowered, and a corrected anion gap can more reliably reflect the true picture.
A typical calculator shows the result and compares it with the laboratory reference range. That range varies somewhat from one lab to another because different analyzers and methods can alter the expected values. For that reason, the same number may be interpreted with different meaning depending on the lab’s reporting standards.
Using an Anion Gap Calculator is helpful when you want a quick, systematic look at a lab result, but the number should not be interpreted in isolation. If bicarbonate is low, for example, the result may point to metabolic acidosis. If bicarbonate is high, the picture may suggest metabolic alkalosis. The calculator is a tool for lab result interpretation, not a diagnosis by itself.
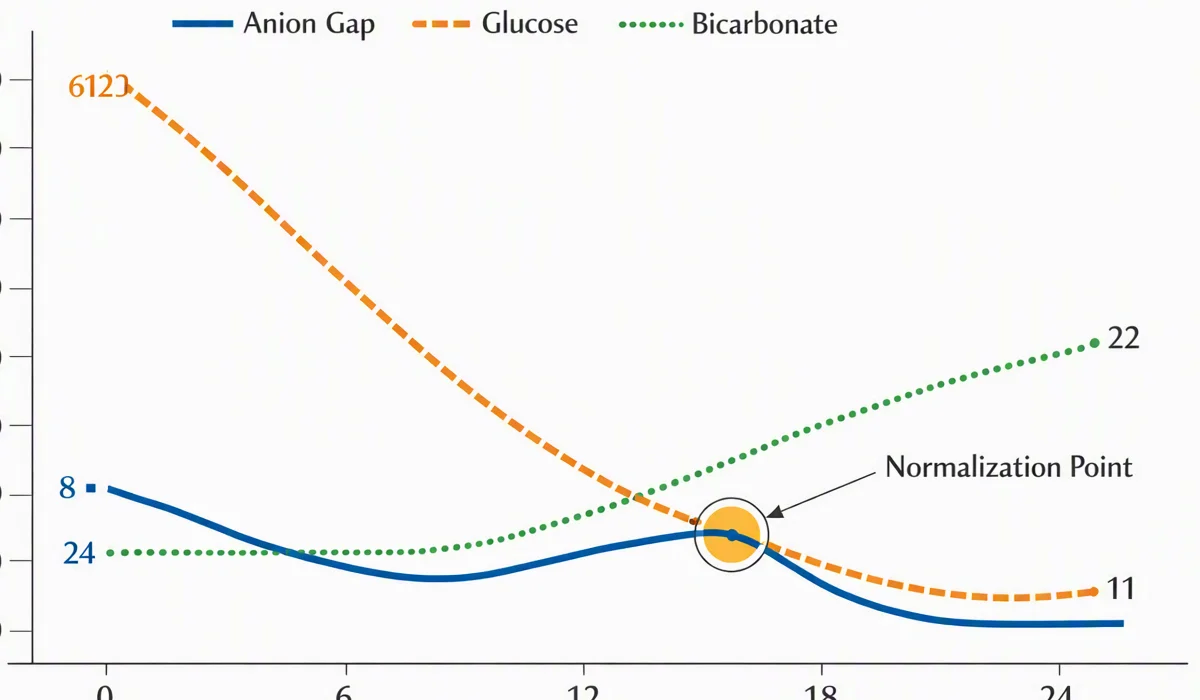
Certain calculators also help users consider the cause of low anion gap findings by prompting consideration of albumin, calcium, and other ions. This is especially helpful when the result seems surprising or when there is an unexplained result that does not fit the clinical picture.
Can Hypercalcemia Lower the Anion Gap?
Yes, hypercalcemia can reduce the anion gap, but it usually does so only slightly. The reason is that elevated serum calcium increases the amount of circulating positive charge from calcium ions, which can narrow the calculated gap between measured cations and measured anions. In theory, this alters the balance of electrolyte balance and may lead to a decreased anion gap.
Still, the effect is often minor and not the most common explanation for a low result. In real-world practice, a low anion gap is much more likely to reflect hypoalbuminemia or another issue than to be caused primarily by hypercalcemia. This is why hypercalcemia is best viewed as one possible contributor rather than the leading cause of low anion gap.
The influence of calcium also depends on other factors such as the patient’s albumin level, kidney status, and whether there is another acid-base abnormality present. Because albumin carries a substantial negative charge through protein binding, a low albumin concentration can hide or intensify the impact of calcium on the final number. In other words, the same calcium level may matter more or less depending on the surrounding chemistry.
From a practical standpoint, if a patient has both hypercalcemia and a low anion gap, the result should not automatically be attributed to calcium alone. The broader differential diagnosis should still include albumin deficiency, paraproteins, medications, and lab-related issues. Hypercalcemia may be part of the story, but it is usually not the whole story.
The Reason Hypercalcemia Typically Has a Minor Effect
To see why hypercalcemia usually has a small effect, it helps to think in terms of measured cations and unmeasured anions. The anion gap is designed to estimate the gap left by ions that are not directly measured on a routine panel. Sodium is the major measured cation, while chloride and bicarbonate are measured anions. Calcium is not always included in the standard calculation, so changes in calcium can influence the balance without dominating it.
Most of the time, the body also responds through physiologic compensation. Shifts in renal handling, bicarbonate balance, and other electrolytes can partially offset changes in calcium-related charge distribution. That buffering effect helps explain why even marked hypercalcemia does not usually create a dramatic low anion gap on its own.
Another practical limitation is laboratory variation. Small differences in analyzer methods, specimen handling, or reporting conventions can produce changes that are comparable in size to the effect of calcium itself. As a result, a slight decrease in the anion gap may reflect ordinary variation rather than a meaningful physiologic change.
That is why a low value should be interpreted carefully. If the result is only mildly below the reference range, hypercalcemia may be a contributing factor, but the number may not have major clinical significance by itself. If the decrease is substantial, another explanation is usually present and should be investigated.
Other Reasons of a Low Anion Gap
When a low anion gap shows up, hypoalbuminemia is one of the earliest reasons to consider. Albumin is a major unmeasured anion, so low levels often lower the gap more than any other common factor. This is why albumin should always be reviewed when interpreting an unexpected result.
Paraproteinemia, including conditions such as multiple myeloma, is another important reason. Abnormal positively charged proteins can act as unmeasured cations and lower the gap. In this setting, the low anion gap may be an early clue that points toward a plasma cell disorder rather than a simple electrolyte issue.
Medication and toxin effects can also be relevant. Lithium toxicity can produce a low anion gap because lithium acts as an unmeasured cation. Bromide interference is another classic reason, since bromide may be misread by some assays as chloride, causing chloride to appear artificially high and the gap to appear lower than it really is.
These causes are generally more common and more clinically important than mild hypercalcemia. That does not mean calcium is irrelevant, but it does mean that a truly low anion gap should prompt a broader review of the electrolyte panel, medications, protein status, and possible assay issues.
When to Suspect a Lab Abnormality
A decreased anion gap should suggest the chance of a laboratory artifact ahead of it is taken as a true physiologic finding. Because the calculation depends on several measured values, even a minor error in sodium, chloride, or bicarbonate can skew the final result. If the number does not fit the patient’s condition, measurement accuracy should be questioned.
Repeat testing is often the first step. A fresh specimen can help show whether the result was due to sample error, sampling problems, contamination, or a transient analytical issue. Repeating the chemistry panel is especially valuable when the low anion gap is surprising or when other values seem discordant.
Interference from substances such as bromide, lithium, or other analytes can also produce misleading results. In some cases, the analyzer may incorrectly read chloride or sodium, resulting in a false low anion gap. This is why clinicians often review the entire lab pattern, not just the final calculated number.
If the finding persists on repeat lab test, then the result is more likely to be real and clinically relevant. At that point, the next step is usually a more thorough metabolic evaluation, including albumin, calcium, kidney testing, and assessment for paraproteins or medication effects.
How to Interpret the Output in Context
The best way to understand a low anion gap is to place it in clinical context. The number alone does not identify an acid-base disorder; it only adds to the overall assessment. For example, a low anion gap with low bicarbonate may suggest a mixed disorder, while a low anion gap with normal bicarbonate may be more consistent with hypoalbuminemia or paraproteinemia.
It is also important to watch for signs of metabolic acidosis or metabolic alkalosis. A high or low bicarbonate level alters the interpretation of the full electrolyte pattern. When bicarbonate is abnormal, the anion gap may aid in identifying whether the disturbance is part of a broader acid-base balance problem or whether it is a separate issue.
Renal function is important as well. Kidney disease can alter bicarbonate handling, modify unmeasured ions, and alter how the body compensates for acid-base shifts. A patient with impaired renal function may show a different pattern than someone with normal kidney function even when the same serum calcium level is present.
In real-world use, the best approach is to combine the number from an Anion Gap Calculator with symptoms, the rest of the electrolyte panel, and any relevant medical history. That helps separate a true physiologic change from a minor variation with little clinical significance.
When You Should Seek Medical Evaluation
Clinical evaluation is essential when a low anion gap appears together with symptoms of hypercalcemia or other alarming findings. These symptoms can include thirst, frequent urination, constipation, nausea, confusion, weakness, or fatigue. When symptoms are present, the chemistry result may indicate a clinically meaningful electrolyte imbalance rather than a benign variation.
Evaluation is also more immediate when there are severe electrolyte abnormalities, especially if multiple values on the electrolyte panel are abnormal at the same time. A markedly abnormal calcium level, major bicarbonate shift, or unusual chloride pattern should not be dismissed.
ECG changes add another layer of concern. Hypercalcemia can affect cardiac conduction, and abnormal cardiac findings increase the need for prompt medical review. If the low anion gap occurs in the setting of heart rhythm symptoms, syncope, or chest discomfort, the situation deserves timely attention.
In general, a medical professional should evaluate persistent or unexplained low anion gap findings, especially if albumin is normal and repeat lab test confirmation shows the same pattern. The goal is to determine whether the result get more info reflects hypercalcemia, a protein abnormality, a medication effect, kidney disease, or another metabolic evaluation issue that needs additional review.
FAQ
Can hypercalcemia lower the anion gap?
Yes, it can. Hypercalcemia can lower the anion gap because calcium acts as a cation that can shift electrolyte balance. However, the effect is usually small, and a low anion gap is more often caused by hypoalbuminemia, paraproteinemia, or lab-related issues than by calcium alone.
How much can calcium change the anion gap?
Calcium usually changes the anion gap only a little. A noticeably low result is rarely explained by calcium alone. If the change seems large, consider albumin, unmeasured cations, measurement error, or another acid-base disorder rather than assuming hypercalcemia is the only cause.
What is the most common reason of a low anion gap?
The most common reason is hypoalbuminemia. Since albumin is a key unmeasured anion, low albumin often lowers the anion gap more than any other factor. This is why albumin correction is helpful in lab result interpretation.
Should albumin be corrected when calculating the anion gap?
Yes, when albumin is low or when the result is unexpectedly decreased, albumin correction is often recommended. A corrected anion gap can provide a more precise view of acid-base balance and can prevent a false impression that the gap is truly low.
In what situations does a low anion gap need further evaluation?
A low anion gap needs further evaluation when it is ongoing, not explained, or accompanied by symptoms, severe electrolyte abnormalities, or abnormal kidney function. It should also be evaluated if there is concern for paraproteinemia, multiple myeloma, lithium toxicity, bromide interference, or a possible laboratory artifact.