How to define the Anion Gap?
The anion gap is a figure calculated from a standard blood test that assists clinicians evaluate the balance of electrolytes in the body. It is based on a routine serum chemistry or electrolyte panel and is used to support assessment of acid-base balance. Although the term sounds highly specialized, the idea is straightforward: the result shows the difference between measured positively charged ions and measured negatively charged ions in the blood.
This difference matters because it can indicate the presence of unmeasured anions or unmeasured cations that are not obvious from a basic panel alone. In clinical practice, the anion gap serves as a diagnostic tool and a quick way to guide result analysis when an acid-base disorder or other metabolic disturbance is suspected.
An anion gap calculator makes this process easier by using common lab values to derive the result in seconds. But the number only becomes useful when you grasp what it means in medical context. A normal result may be comforting, while an abnormal one can point toward issues such as metabolic acidosis, low albumin, or other conditions that call for further review.
Anion Gap Calculation and Formula
The standard anion gap equation relies on lab-measured values from the blood, specifically serum sodium, serum chloride, and serum bicarbonate. The most common anion gap formula is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Some doctors use a variation that includes potassium, but today’s calculators use the simpler version above because it is widely accepted and useful for everyday interpretation.
Here is the core logic behind the equation:
- Sodium represents the principal measured cation. Chloride and bicarbonate represent the principal measured anions. The gap shows the balance between measured positive and negative charges.
When you calculate the anion gap, you are not finding a gap in the literal sense. You are determining the amount of charge carried by unmeasured substances in the blood. That is why the anion gap equation is so useful for identifying an acid-base disorder and for recognizing patterns in a serum chemistry result.
A higher-than-expected result suggests additional unmeasured acids or other compounds, while a reduced result can suggest a loss of negatively charged proteins or a measurement problem. Because of that, correct use of the anion gap formula depends on the complete lab picture, not just one isolated number.
How the Anion Gap Calculator Works
An anion gap calculator is built to streamline the math and limit manual errors. You provide the input values from the electrolyte panel, and the calculator carries out the calculation steps automatically. In most cases, you supply sodium, chloride, and bicarbonate values, then the tool gives the anion gap along with a reference range or interpretation note.
The process usually goes like this:
- Enter the sodium value from the blood test. Input the chloride value. Enter the bicarbonate value. Examine the calculated result and assess it with the reference range.
Many users rely on an online calculator because it supports quick pattern recognition during result analysis. It is especially useful when reviewing an electrolyte panel in a busy clinical setting or when trying to understand whether a lab pattern suggests a broader metabolic issue.
Even though the calculator is simple, the numbers still need context. A value that falls within the reference range may still be abnormal if albumin is low or if another condition is changing the baseline. That is why the calculator is best viewed as a first step in interpretation, not the final answer.
In practical use, the calculator helps identify whether the result fits a typical normal anion gap pattern or whether further review is needed. It can also support decision-making when the goal is to understand possible causes of metabolic acidosis or other acid-base changes.
Expected Anion Gap Range and What Influences It
The normal range for the anion gap differs slightly by laboratory because of differences in assay methods, analyzer calibration, and reporting practices. Here lab variation is important. A result that is deemed normal in one setting may be a bit different in another, so the lab’s own reference range should take priority.
Several factors can alter the number:
- Albumin: Because albumin is a major unmeasured anion, lower levels can reduce the measured gap. Lactate: Higher lactate can widen the gap because it adds unmeasured anions. Lab variation: Alternative instruments and methods may produce slightly different values.
Albumin is especially significant because it is one of the primary contributors to the anion gap. When albumin is low, the normal anion gap may appear artificially reassuring. In those cases, an albumin correction or albumin adjustment may be needed to estimate a more accurate corrected anion gap.
That matters because a patient can have a meaningful acid-base problem even if the raw number seems normal. Because of this, interpreting the value without checking albumin can lead to missed abnormalities. Similarly, elevated lactate can shift the result upward even before other abnormalities are obvious.
Elevated Anion Gap: Common Causes
A high anion gap usually indicates the presence of undetected acids in the blood. The main clinical concern is acid-base disturbance, where acid builds up or bicarbonate is depleted in a way that increases the calculated gap.
Typical causes include:
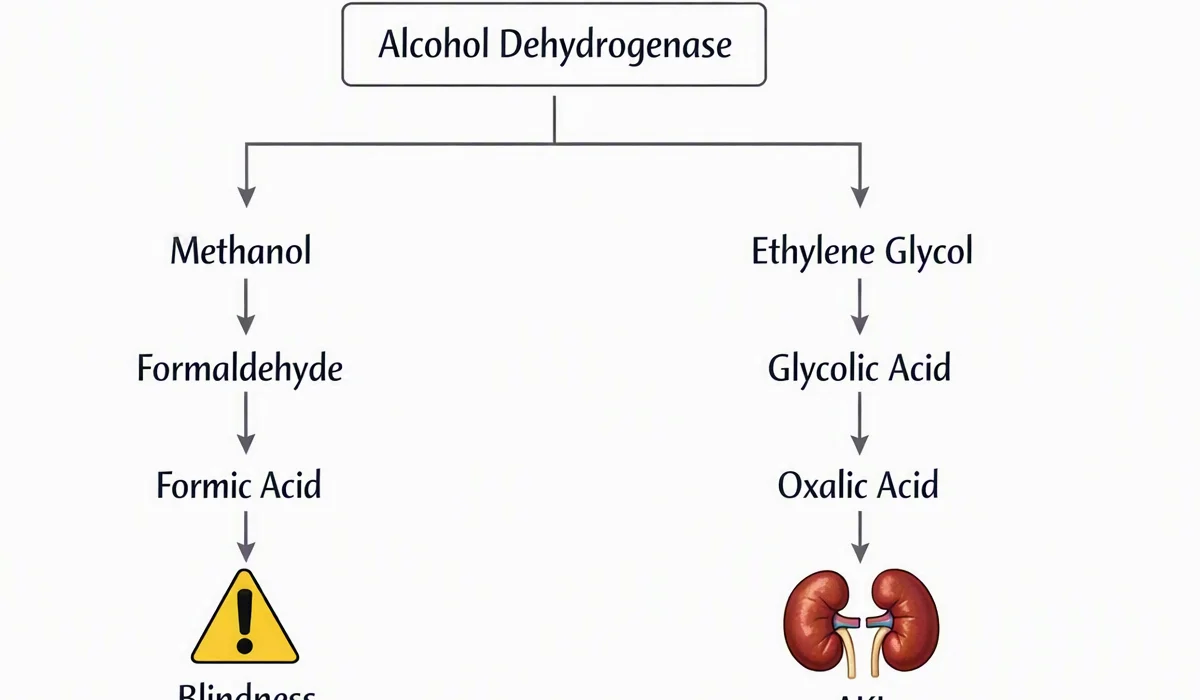
- Lactate acidosis, often linked to reduced tissue oxygen delivery, severe illness, or decreased lactate clearance. Ketone-related acidosis, which can occur when ketone bodies rise during insulin deficiency, starvation, or other metabolic stress. Impaired kidney function, where reduced acid excretion causes acids to build up. Poisoning, including certain substances that generate unmeasured acids or interfere with normal metabolism.
This matters because they point to different treatment pathways. For example, lactic acid buildup suggests a search for tissue hypoperfusion or severe infection, while ketoacidosis indicates abnormal fat metabolism and requires a different management approach. Kidney failure may cause acid retention over time, and poisoning can produce a dangerous metabolic picture that needs urgent assessment.
A high value is not a diagnosis by itself. It is a clue that should be considered alongside symptoms, history, and the rest of the blood test results. In many cases, it prompts more testing to identify the underlying cause and to determine how severe the metabolic disturbance is.
Low Anion Gap: Frequent Causes
A low anion gap is less common than a high one, but it can still be medically significant. One of the most common explanations is hypoalbuminemia, because albumin is a negatively charged protein that contributes to the normal gap. When albumin falls, the calculated value can fall with it.
Other frequent causes include:
- Paraproteinemia, where abnormal proteins in the blood alter the balance of measured and unmeasured ions. Lab error, including specimen issues or measurement problems that distort the reported electrolytes.
Hypoalbuminemia is especially relevant because it can mask a serious condition if the result is interpreted without an albumin correction. In some patients, the corrected value may reveal a more significant disorder than the unadjusted number suggests. This is why a corrected anion gap can be more informative than the raw calculation alone.
Paraproteinemia should be considered when abnormal proteins are present, particularly if other findings do not match the apparent result. And because lab error is always possible, an unexpected low result should be reviewed carefully before drawing conclusions. Repeating the test or checking the full electrolyte panel may help confirm whether the number is real.
Clinical Role of the Anion Gap in Acid-Base Disorders
The anion gap is especially useful when used as part of a broader assessment of acid-base disorders. It helps differentiate different types of metabolic acidosis and supports the work of pattern recognition when reviewing a blood test, electrolyte panel, and serum chemistry results together.
In practice, the anion gap helps clarify questions such as:
- Could the acidosis be the acidosis related to accumulation of unmeasured acids? Does the pattern suggest bicarbonate loss instead? Is the gap elevated enough to prompt looking for lactate, ketones, toxins, or renal dysfunction?
Another important concept is the delta gap, which examines the change in anion gap with the change in bicarbonate. This can help detect mixed disorders, where more than one metabolic process is happening at the same time. That is useful because a patient may have a high anion gap acidosis and another acid-base problem concurrently.
A blood gas is often interpreted alongside the anion gap to offer a fuller picture of acid-base status. The blood gas shows pH and respiratory compensation, while the anion gap helps pinpoint the underlying metabolic component. Together, they improve clinical significance and help with cause assessment.
This is why the anion gap remains a practical diagnostic tool: it turns a simple lab calculation into a helpful guide for anion gap clinical significance evaluating complex metabolic disturbances.
Ways to Interpret Outputs Carefully
Good medical interpretation requires more than checking HAGMA differential diagnosis one result. The anion gap should be reviewed in the context of clinical symptoms, the entire electrolyte panel, medication history, kidney function, and any additional signs of illness. A result that appears abnormal may be explained by timing, fluid status, protein changes, or measurement differences.
Safe interpretation involves several steps:
- Check the values used in the calculation. Confirm whether the lab’s reference range changes from other sources. Evaluate albumin and consider albumin adjustment if needed. Assess for signs of electrolyte imbalance or metabolic acidosis. Identify clinical clues that support or weaken a suspected cause.
If the result suggests a major abnormality, a medical evaluation is important. This is especially true when symptoms such as confusion, rapid breathing, dehydration, vomiting, or severe weakness are present. The anion gap is helpful, but it does not replace a full assessment of the person and the illness.
In other words, the number should guide the next step, not serve as the final conclusion. Using the calculator result with clinical context improves accuracy and reduces the risk of missing an important problem.
FAQ
What does the anion gap calculator do?
The anion gap calculator is used to calculate the anion gap from common blood test values, usually sodium, chloride, and bicarbonate. It helps with interpretation of acid-base balance and can point toward a metabolic disturbance such as metabolic acidosis.
What is the formula for calculating the anion gap?
The most common anion gap equation is: sodium minus the sum of chloride and bicarbonate. In short, the anion gap formula is sodium − (chloride + bicarbonate). Some versions may include potassium, but the simpler formula is widely used.
How is a typical anion gap result?
The expected range is influenced by the testing facility and technique used, so the listed range on the lab report should be checked initially. A result in the expected range generally implies no major build-up of hidden acids, but protein levels and measurement differences can influence the value.
Why does there be a high anion gap?
A elevated anion gap is often the result of metabolic acidosis from conditions such as excess lactic acid, ketone buildup, renal failure, or poisoning. These causes contribute unmeasured acids to the blood and elevate the calculated result.
Can a low anion gap signal a medical problem?
It can. A reduced anion gap can be associated with low albumin, protein abnormalities, or measurement error. It may also reflect other alterations in electrolytes or proteins, so it should be reviewed in clinical context rather than overlooked.