Understanding the Anion Gap and Its Importance
The anion gap is a valuable lab-calculated value used to detect the cause of metabolic acidosis and other disturbances in electrolytes. In the emergency department, it acts as a quick triage tool for acid-base balance problems and helps providers refine a broad differential into a focused diagnostic algorithm.
An anion gap calculator is valuable because the underlying concept is simple, but the interpretation is not. A patient may present with an apparently mild metabolic derangement, yet the pattern of serum electrolytes can reveal significant illness such as lactic acidosis, ketoacidosis, toxic ingestion, or renal failure. The gap represents the difference between measured cations and measured anions, which reflects unmeasured anions in the blood.
For emergency medicine, the anion gap is not just a number. It is a piece of clinical decision support that helps identify whether the patient likely has high anion gap metabolic acidosis, normal anion gap metabolic acidosis, or another acid-base disorder entirely. It also guides whether to obtain additional studies such as a venous blood gas, lactate, ketones, toxicology testing, or an osmolar gap.
How to Determine the Anion Gap
The usual anion gap formula is based on the primary measured electrolytes: sodium, chloride, and bicarbonate. One common form is:
Anion gap = Sodium − (Chloride + Bicarbonate)
A few laboratories and references may also include potassium, but in emergency practice, the sodium-based formula is the most common because it is simple, fast, and widely available on the basic metabolic panel. The result indicates the amount of anion deficit from unmeasured ions.
For example: if sodium is 140, chloride is 104, and bicarbonate is 20, the calculation is 140 − (104 + 20) = 16. That value may be within normal limits or slightly high depending on the lab reference range and the patient’s clinical context.
An anion gap calculator automates this diagnostic calculation, minimizing manual errors during time-sensitive critical care evaluation. It also helps clinicians quickly compare sequential results from an electrolyte panel when monitoring a patient’s response to treatment.
Using the Anion Gap Calculator in Emergency Medicine
In acute care, the calculator is particularly valuable when a patient has unexplained tachypnea, altered mental status, hypotension, vomiting, dehydration, or concern for toxicity. It is typically used alongside the metabolic panel, point-of-care testing, and at times blood gas analysis.
Bedside testing can provide immediate sodium, chloride, and bicarbonate values that allow clinicians to identify metabolic abnormalities early. This matters when the patient may be deteriorating and decisions about fluids, insulin, bicarbonate, antidotes, or dialysis need to be made promptly.
Practical use in the ED often follows this sequence:
- Review the electrolyte panel and calculate the anion gap. Determine whether the patient has metabolic acidosis on a venous blood gas or arterial sample. Evaluate whether the pattern suggests increased anion gap metabolic acidosis or normal anion gap metabolic acidosis. Consider confirmatory tests such as lactate, beta-hydroxybutyrate, ketones, renal function, or toxicology studies.
The value of the calculator is not in isolation, but in the way it improves result interpretation and supports early recognition of dangerous disease. In a rapid ED workflow, it is one of the most efficient ways to screen for major acid-base pathology.
Standard, Increased, and Low Anion Gap Results
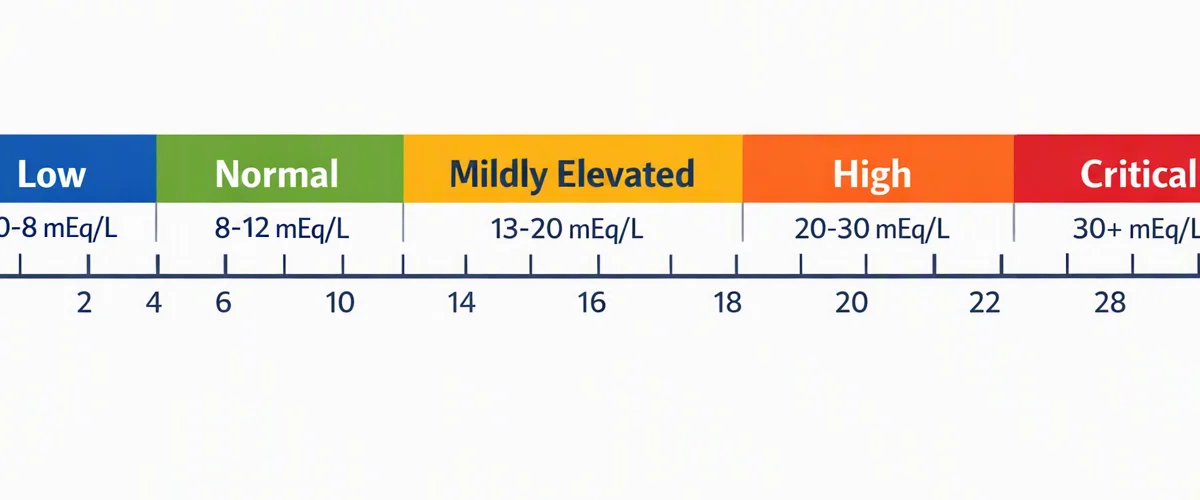
A normal anion gap usually suggests that any acidosis present is caused by loss of bicarbonate or chloride retention rather than by build-up of unmeasured acids. However, “normal” depends on the laboratory method and comparison range, so clinicians should always interpret the value using site standards.
Elevated anion gap metabolic acidosis suggests an excess of unmeasured acids in the circulation. This is the result that often leads to urgent evaluation for lactic acidosis, ketone-related acidosis, toxic alcohols, and renal failure. It is a key signal in metabolic assessment when a patient appears ill or has abnormal vital signs.
A reduced anion gap is less common and can be overlooked. It may occur with severe hypoalbuminemia, laboratory artifact, or occasionally other less common clinical conditions. Although a low value is not usually the main emergency concern, it should prompt reassessment of the test result and the broader acid-base disorder.
For practical anion gap clinical significance interpretation, the anion gap should be seen as a pattern based tool rather than a stand-alone diagnosis. The presence of a normal or abnormal gap helps direct the next step in the diagnostic pathway, not replace it.
Frequent Causes of a High Anion Gap
A number of conditions can result in high anion gap metabolic acidosis, and the emergency provider should think in terms of rapid exclusion of critical causes. The most common and important include lactic acidosis, ketoacidosis, and exposure to toxic alcohols.
Lactic acidosis often arises in shock, hypoperfusion, seizures, severe infection, or tissue ischemia. In the ED, this is a significant concern in patients with concern for sepsis, hypotension, or respiratory compromise. The anion gap may climb as lactate accumulates and depletes bicarbonate during buffering.
Ketoacidosis occurs when ketone bodies accumulate as organic acids. Diabetic ketoacidosis is the typical emergency presentation, but starvation or alcoholic ketosis can also play a role. The bicarbonate level often falls markedly, and the anion gap rises because ketones are unmeasured anions.
Toxic alcohols are another important cause of a high gap. Ethylene glycol and methanol are especially important because they can result in serious organ injury and may initially present with nonspecific symptoms. In these cases, the anion gap may become elevated later in the course, so timing matters. An elevated gap with suspicion of ingestion should prompt consideration of an osmolar gap and immediate toxicity screening.
Other causes may exist, but these three are the top priorities in the ED because they are rapidly evolving and potentially reversible with prompt treatment.
Common Causes of Normal Anion Gap Acidosis
Normal anion gap acidosis is often linked to reduced bicarbonate or impaired acid secretion. The hallmark lab pattern often includes a drop in bicarbonate with a compensatory increase in chloride, creating hyperchloremic metabolic acidosis.
Diarrhea is a frequent cause. Loss of bicarbonate through the gut can decrease bicarbonate levels while chloride increases to keep electrical balance. This clearly shows how the shift in chloride helps maintain balance on laboratory reports while the patient stays metabolically acidotic.
RTA is another important cause. In this condition, the kidneys cannot adequately acidify the urine or reabsorb bicarbonate, leading to ongoing acidosis despite a normal anion gap. It is important to recognize this because it may suggest an underlying or chronic kidney issue rather than a transient illness.
This acid-base disorder can also occur after large-volume saline administration, though the primary causes to consider to keep in mind remain diarrhoea, RTA, and bicarbonate loss through the kidneys. A careful review of fluids, medications, and recent illness helps distinguish these patterns.
How the protein albumin Influence the Anion Gap
the protein albumin is the most important not directly measured anion in plasma, so a reduced albumin level can spuriously reduce anion gap online calculator the anion gap. That matters because a patient may have a meaningful acidosis that appears milder on the initial calculation.
For this reason clinicians often use a anion gap correction when hypoalbuminemia is present. A common approach is to adjust the measured gap upward when albumin is below normal, which helps uncover hidden excess acids. Different institutions may use different correction methods, but the principle is the same: low albumin can conceal a dangerous elevation.
This correction is especially relevant in critical care and in patients with hepatic disease, malnutrition, inflammation, or chronic illness, where low albumin is frequent. Without correction, the anion gap may miss the true degree of metabolic derangement.
In practice, a corrected calculation strengthens lab interpretation and can detect a masked high gap when the raw result appears falsely normal. For that reason the anion gap calculator is most useful when combined with albumin data rather than used alone.
Sequential Analysis in the ED
Evaluating the anion gap in the emergency department should follow a structured approach. The goal is to detect the underlying acid-base disorder quickly and see whether immediate treatment is needed.
Step 1: Check the chemistry values. Inspect sodium, chloride, and bicarbonate from the basic metabolic panel or point-of-care source. Make sure the result is reasonable and not obviously affected by laboratory error.
Next: Assess whether the patient has metabolic acidosis on a venous blood gas or other blood gas measurement. A low bicarbonate alone is not enough; pH and respiratory compensation help outline the full picture.
Step 3 — Classify the gap as normal, elevated, or low. If elevated, think first about lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. If normal, focus on bicarbonate loss or chloride excess.
Step 4 — If the presentation suggests ingestion, check the osmolar gap. An elevated osmolar gap with metabolic acidosis heightens concern about toxic alcohol exposure, especially when clinical findings are unclear.
Step 5 — Combine all findings with the story. The same lab result means something different in a stable patient with mild diarrhea than in a hypotensive patient with altered mentation and respiratory distress.
This stepwise method is essentially a bedside diagnostic algorithm that integrates the calculator with patient status, blood gas data, and additional labs. It is a practical example of metabolic evaluation in real-time care.
Limitations and Problems of the Calculator
Like any diagnostic calculation, the anion gap calculator has limitations. Small differences in lab methods can create measurement variation, so the exact normal range can vary between institutions and analyzers.
Laboratory error can also mislead interpretation. Hemolysis, specimen handling issues, or inconsistent repeat values may produce a result that does not fit the clinical picture. When the number and the patient do not match, repeat testing and correlation with other data are essential.
The calculator does not replace clinical context. Even a modest elevation can be significant in an unstable patient with toxicity, while a higher result may be long-standing or partially compensated in a patient with known kidney disease. The anion gap should therefore be interpreted as part of the full clinical context rather than as a stand-alone trigger.
Other pitfalls include overlooking albumin, treating every elevated gap as a single-cause problem, or failing to look for a mixed disorder. The most accurate interpretation usually comes from integrating the anion gap with blood gas results, renal labs, ketones, lactate, and toxin screening when indicated.
When to Escalate Evaluation or Treatment
Escalate without delay when the anion gap suggests a serious condition such as sepsis, renal failure, or poisoning. These are not merely abnormal lab values; they are urgent emergencies that can worsen quickly without treatment.
In suspected sepsis, an elevated gap plus elevated lactate or hemodynamic instability should prompt rapid resuscitation, cultures, antimicrobial therapy, and source evaluation. In renal failure, worsening acidosis may require nephrology input, close electrolyte monitoring, and possible renal replacement therapy depending on the overall picture.
For suspected poisoning, especially with toxic alcohols, ethylene glycol, or methanol, do not delay for confirmatory results if the clinical suspicion is high. The combination of acidosis, elevated gap, and possible osmolar gap can warrant immediate antidotal treatment and consultation with toxicology.
Escalation is also appropriate when the patient has worsening mental status, respiratory fatigue, shock, or rapidly changing laboratory values. The calculator should direct the next step, not delay it.
Frequently Asked Questions
What is the anion gap calculator used for?
The anion gap calculator is used to swiftly estimate the anion gap from serum sodium, chloride, and bicarbonate values. In emergency medicine, it helps clinicians detect metabolic acidosis, classify acid-base disorders, and decide whether further evaluation for lactic acidosis, ketoacidosis, toxic alcohols, or renal failure is needed.
What is the normal range for the anion gap?
The usual range depends on the measurement method and calibration standard used by that laboratory. Because measurement techniques vary, clinicians should interpret the value using the lab-specific range rather than relying on a single cutoff. In practice, the result is best understood in together with the patient’s symptoms, bicarbonate level, and overall acid-base balance.
How is a corrected anion gap for albumin?
To estimate a corrected anion gap, clinicians adjust the measured result upward when albumin is low because hypoalbuminemia can hide a true elevation. The exact correction method can vary, but the goal is the same: account for the effect of low albumin on the gap so that significant metabolic acidosis is not missed. This is especially useful in patients with long-term illness, liver disease, or critical illness.
What leads to a high anion gap in emergency medicine?
The most important causes of high anion gap metabolic acidosis in emergency medicine include lactic acidosis, ketoacidosis, and toxic alcohols such as ethylene glycol and methanol. Other important causes include sepsis and renal failure. The anion gap should be interpreted with blood gas results, lactate, ketones, renal studies, and the patient’s overall status.
When should an osmolar gap be checked with anion gap results?
An osmolar gap should be checked when there is concern for ingestion, especially if the patient has unexplained acidosis, altered mental status, or a history that suggests possible exposure to toxic alcohols. It is particularly useful when evaluating possible ethylene glycol or methanol poisoning. In the ED, the osmolar gap adds another layer of toxicology screening to the broader metabolic evaluation.