How the Anion Gap Helps in Salicylate Poisoning
The anion gap is a useful clue in the assessment of salicylate poisoning, but it should never be treated as a isolated diagnosis. In toxicology, the gap helps reveal hidden acids in the blood and informs the broader acid-base balance assessment. Because aspirin exposure can produce more than one disturbance at the same time, the anion gap is often part of a broader laboratory interpretation rather than a single decisive number.
Classic aspirin toxicity often creates a mixed acid-base disorder. Initially, salicylates stimulate the respiratory center, leading to respiratory alkalosis through compensatory hyperventilation. With worsening toxicity, organic acids and impaired metabolism contribute to metabolic acidosis. The result is a pattern that can look confusing if you focus only on one value. The anion gap becomes a diagnostic clue that helps link the serum chemistry findings to the underlying toxicology evaluation.
Salicylates interfere with cellular metabolism and can disrupt oxidative phosphorylation, which promotes the accumulation of organic acids. These metabolic derangements lower buffering capacity and may increase the anion gap. At the same time, patients may present with tachypnea, nausea, vomiting, altered mental status, or other signs of systemic toxicity. In this setting, the anion gap supports clinical correlation rather than replacing it.
A normal or only mildly elevated anion gap does not exclude salicylate poisoning, especially when the acid-base pattern is evolving.
How to Use an Anion Gap Calculator
An anion gap calculator is a handy tool for rapid laboratory assessment during emergency assessment and poisoning workup. The basic calculation usually uses serum sodium, serum chloride, and serum bicarbonate. In its common form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Using the calculator begins with correct serum chemistry values. First, enter the sodium concentration. Then, add the chloride and bicarbonate concentrations. Take away that sum from sodium to obtain the gap. This basic anion gap calculation can rapidly identify whether there is an unexpected accumulation of unmeasured anions.
In suspected salicylate poisoning, the calculator should be used as part of a broader diagnostic workflow. Look at the numerical value, but also consider the patient's symptoms, respiratory rate, mental status, and other evidence of electrolyte abnormalities. A elevated number may support systemic toxicity, while a borderline result may still be clinically important if the complete picture suggests aspirin exposure.
It is also important to compare the calculated result with the laboratory’s reference range if one is provided. Different institutions may use slightly different methods or reference values, which affects laboratory interpretation. The goal is not simply to identify an abnormal number, but to use that number to guide toxicology evaluation and further testing.
Classic Laboratory Patterns in Aspirin Toxicity
Aspirin toxicity typically presents with its mixed and occasionally shifting lab profile. A frequent early pattern is respiratory alkalosis with a decreased or dropping bicarbonate, followed by metabolic acidosis as salicylate burden rises. This is why an arterial blood gas is often helpful. The arterial blood gas offers direct information about pH, carbon dioxide, and bicarbonate status, helping confirm the presence of a mixed acid-base imbalance.
Patients with salicylate poisoning may show a reduced carbon dioxide level because of hyperventilation. At the same moment, the bicarbonate may be decreased due to the metabolic component. The anion gap may increase as acids accumulate. This creates a diagnostic challenge: a patient can have near-normal pH if respiratory alkalosis and metabolic acidosis counteract one another. That is one reason clinicians should avoid relying on pH alone when evaluating a possible toxic ingestion.
Lactate may also be elevated in aspirin toxicity. However, elevated lactate does not by itself explain the disturbance by itself. Salicylates can disrupt energy production and contribute to acid generation beyond simple tissue hypoperfusion. Therefore, lactate is a helpful part of the poisoning workup, but it should be interpreted together with the anion gap, arterial blood gas, and the rest of the clinical data.
Another important pattern is that the severity of symptoms does not consistently reflect the first available lab values. Early testing may miss the full metabolic derangement. Repeat assessment is often necessary because the toxicology evaluation can progress swiftly. A patient may progress from a relatively subtle pattern to severe systemic toxicity over a short period of time.
Corrected Anion Gap and albumin adjustment
Albumin is the chief unmeasured anion in the blood, so low albumin can make the anion gap seem deceptively typical. This is especially relevant in hypoalbuminemia, where the standard gap may miss the true burden of unaccounted-for acids. For that reason, a corrected anion gap is often more accurate when acid-base interpretation is important clinically.
In suspected salicylate poisoning, albumin adjustment helps prevent overlooking a hidden high-gap state. If albumin is reduced, the measured anion gap should be corrected before concluding that the serum chemistry is comforting. This step enhances diagnostic accuracy and minimizes the chance of false reassurance in a patient with possible toxic ingestion.
Corrected values are particularly useful when other findings point toward poisoning despite a near-normal number. For example, a patient may have tachypnea, nausea, ringing in the ears, and an arterial blood gas showing mixed acid-base disorder, yet the initial gap is only modestly elevated. In that setting, albumin correction can uncover a more meaningful abnormality and improve acid-base interpretation.
Albumin adjustment is not only about mathematics. It is about correlating the laboratory pattern to the patient's physiologic state. In clinical practice, the corrected anion gap helps bring together acid-base balance, serum chemistry, and toxicology evaluation so the clinician can identify systemic toxicity earlier.
When a High Anion Gap Causes Concern
A high anion gap within the right clinical context should signal a significant underlying condition. In salicylate poisoning, this may suggest accumulated organic acids and impaired metabolism. However, the differential diagnosis is extensive, and the gap should call for a structured evaluation rather than an assumption of one cause.
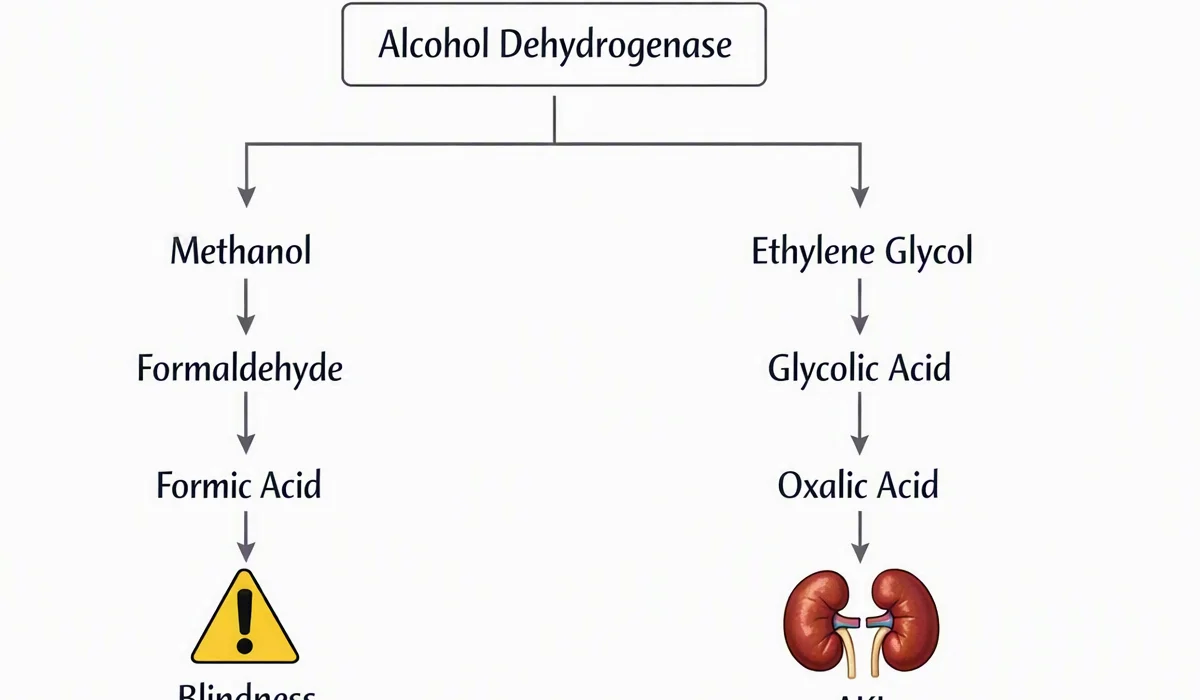
Other common explanations include ketone buildup from diabetes, fasting, or alcohol-related situations, and impaired kidney function, where acid clearance is reduced. A toxic exposure can also produce a high gap, including salicylates, methanol, ethylene glycol, or other agents. This is why the anion gap calculator is best used as a screening and triage tool within a larger diagnostic workflow.
When the gap is elevated, ask whether the pattern aligns with the story. more info Does the patient have respiratory alkalosis and metabolic acidosis together? Are there symptoms that indicate aspirin exposure? Is there evidence of dehydration, reduced kidney function, or glucose abnormalities that might suggest another explanation? These questions strengthen clinical correlation and prevent misinterpretation.
The anion gap also matters because a increasing value can signal worsening metabolic derangement. Even if the patient initially appears unchanged, an increasing gap along with worsening symptoms may indicate advancing systemic toxicity. In that setting, repeat testing and rapid toxicology evaluation become even more important.
Clinical Follow-up Steps Once You Calculate the Gap
Following calculation of the gap, the following step is to connect the result to the overall poisoning workup. If salicylate poisoning is suspected, obtain a salicylate level as soon as possible. This matters because the anion gap alone cannot quantify exposure or severity. A level helps establish the diagnosis, monitor trends, and guide treatment decisions.
Assess the full set of electrolytes, including sodium, chloride, bicarbonate, potassium, and any other available serum chemistry markers. Electrolyte abnormalities are common in toxic states and can alter acid-base balance. If the patient is clinically concerning, a repeat blood gas and repeat chemistry panel may be needed to track progression.
Repeat testing is particularly valuable when the presentation is early or unclear. Salicylate concentrations may rise after the initial sample if absorption continues, especially with enteric-coated products or delayed gastric emptying. The acid-base disorder may also evolve, shifting from mixed respiratory alkalosis and metabolic acidosis toward more severe acidemia.
Contact poison control early when aspirin toxicity is possible. Expert guidance can help analyze the laboratory pattern, recommend follow-up testing, and support management decisions. Poison control is especially useful when the case interpretation is complicated by coexisting disease, uncertain timing, or ambiguous lab results.
At this stage, the key is integration. The anion gap calculator provides one data point, but toxicology evaluation depends on the whole picture: symptoms, lab trends, salicylate level, arterial blood gas findings, and the clinical course.
Constraints of the Anion Gap in Salicylate Poisoning
This anion gap has real importance, but it also has important drawbacks. A normal anion gap does not eliminate salicylate poisoning, especially in the early stage of poisoning or in patients with low albumin or mixed disorders that obscure the expected result. This is one of the most important reasons not to rely on the calculator alone.
Incorrect confidence can happen when providers anticipate a dramatic gap rise and ignore alarming symptoms. In early stages, a respiratory alkalosis pattern may dominate, and the metabolic component may not yet be clearly apparent. A patient can therefore seem sick while the gap remains normal or slightly elevated. That is why the result must be assessed with clinical reasoning rather than treated as a test for exclusion.
One more constraint is that acid-base analysis can be influenced by concurrent illness. Kidney failure may alter baseline chemistry. Ketone buildup can by itself elevate the gap. Other metabolic disturbances can mask the usual pattern of aspirin toxicity. In these situations, the gap remains valuable, but only as part of a more comprehensive toxicology evaluation.
The best use of the anion gap is as a helpful diagnostic clue. It can reveal unseen acids, aids in spotting complex acid-base imbalance, and triggers additional evaluation. But it is not definitive. Good clinical judgment stays essential, especially when the presentation raises concern for systemic toxicity but the numbers are not clear-cut.
Common Questions on Anion Gap and Salicylate Toxicity
How does anion gap calculator help in salicylate poisoning?
A anion gap calculator helps by rapidly indicating whether there is an unexpected increase in undetected acids, which can reinforce suspicion for salicylate poisoning. It is especially useful when used with serum chemistry, an arterial blood gas, and the clinical picture. In toxicology, it serves as an initial diagnostic clue rather than a final answer.
Can salicylate poisoning occur with a normal anion gap?
Yes. A normal anion gap result can appear in the early stages of poisoning, in a mixed acid-base disturbance, or when low albumin masks the abnormality. This is why a normal result should not create false reassurance. If the history or presentation suggest salicylate toxicity, additional testing and clinical correlation are still needed.
Why do patients with aspirin toxicity often have both respiratory alkalosis and metabolic acidosis?
Aspirin increase breathing, leading to respiratory alkalosis, while anion gap clinical significance also impairing metabolism and producing organic acids, which causes metabolic acidosis. This mix creates a mixed acid-base disorder that can be seen on the arterial blood gas and in the anion gap. The pattern is a hallmark of toxicology evaluation for salicylate exposure.
Should the anion gap be corrected for albumin in suspected poisoning?
Yes, especially if albumin is low. Albumin contributes to the unmeasured anions in blood, so hypoalbuminemia can hide a meaningful gap elevation. A corrected anion gap improves acid-base interpretation and reduces the chance of missing toxic ingestion.
What labs should be checked after finding a high anion gap in suspected salicylate toxicity?
Check a salicylate level, complete electrolytes, bicarbonate, kidney function, lactate, and an arterial blood gas. Follow-up testing may be needed because the pattern can change over time. If the case is concerning, contact poison control and continue the poisoning workup with careful clinical judgment.