What the Anion Gap Measures
The anion gap is a practical way to determine the discrepancy between routinely measured electrolytes in the blood and the unseen charged particles that help maintain acid-base balance. Clinically, it is most often used to support evaluation of metabolic acidosis and other acid-base disorders.
An anion gap calculator uses standard laboratory values such as sodium, chloride, and bicarbonate to assist in detecting whether there are excess unmeasured anions in the plasma. In everyday practice, this is a useful part of clinical interpretation because it can point toward a specific metabolic derangement even before the full picture is known.
The basic idea is simple: sodium represents most of the measured positive charge, while chloride and bicarbonate represent primary measured negative charges. The gap shows the relationship between these laboratory values and https://anion-gap-calculation.com/case-studies/sepsis-lactic.html the unseen ions that are not directly reported on a standard electrolyte panel.
Although the number itself is only one piece of the puzzle, it is a valuable screening tool for identifying an abnormal acid-base state and guiding a more focused diagnostic algorithm. In settings such as critical care, the anion gap can help identify whether a patient likely has an acid-base disturbance that needs immediate workup.
How to Work with an Anion Gap Calculator
To operate an anion gap calculator, begin with a serum chemistry panel and enter the input values for sodium, chloride, and bicarbonate. Most calculators also support entry of serum albumin, which is essential when you want an albumin-corrected anion gap.
The calculator applies the anion gap formula and produces a value that can be compared with the expected reference range. A result above the expected range may point to excess acids or other unmeasured anions, while a normal value does not fully exclude an acid-base disorder.
For clinical use, the process should be systematic:
- Check the basic electrolyte values on the serum chemistry panel. Determine whether serum albumin is available. Enter the input values carefully to avoid transcription mistakes. Examine the calculated anion gap in the context of the patient’s symptoms and other laboratory values. Decide whether an albumin correction is needed before interpreting the result.
The calculator is best used as a clinical decision-support aid, not as a standalone diagnosis. A single number does not replace bedside assessment, medication review, or more advanced acid-base analysis. Instead, it helps clinicians recognize patterns that warrant a closer look.

Anion Gap Formula and Calculation Methods
The classic anion gap formula is commonly written as:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain laboratories and references include potassium in the equation:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
Each version are used in clinical practice, but the sodium-only version is more common because potassium contributes relatively little to the total. Still, it helps to know which method your calculator uses so you can match the result with the correct reference range.
The corrected anion gap is most useful when serum albumin is low. Because albumin is a major unmeasured anion, low levels can make the uncorrected gap appear falsely normal. In that setting, albumin correction helps reveal hidden acid accumulation that might otherwise be missed.
For practical use, the calculator should explicitly show which method is being applied. That prevents confusion when the result is reviewed alongside other electrolytes and supports more reliable diagnostic support in real-time care.
Normal Anion Gap Range & Its Interpretation
The usual reference range for the anion gap depends on the laboratory method, analyzer platform, and whether potassium is included. Because of this, there is not a single standard normal number. Rather, clinicians should interpret the result using the laboratory-specific range reported with the patient’s laboratory values.
A normal anion gap often suggests that the balance between measured cations and anions is in the normal range, but it does not rule out disease. A patient may still have normal anion gap metabolic acidosis, especially if there is a compensatory rise in chloride.
A high anion gap indicates accumulation of acids or other unmeasured substances. That finding is particularly important when evaluating possible metabolic acidosis. However, the degree of elevation may be masked by hypoalbuminemia or affected by lab variation.
Clinical review should always consider the full clinical picture:
- Does the patient show acidemia on blood gas testing? Are there signs of shock, hypoperfusion, or toxin exposure? Do the electrolytes show concurrent hyperchloremia? Is the bicarbonate reduced in a way that fits the expected pattern?
These questions turn a raw value into meaningful clinical interpretation.
Origins of high anion gap metabolic acidosis
high anion gap metabolic acidosis occurs when acids accumulate at a faster rate than the body can clear them or neutralize them. This results in a elevation in unmeasured acid anions and a drop in serum bicarbonate.
Typical causes include lactic acidosis, ketoacidosis, and renal failure. In lactic acidosis, impaired oxygen delivery or mitochondrial dysfunction leads to lactate accumulation. In ketoacidosis, ketone bodies accumulate in states such as diabetic decompensation, starvation, or alcohol-related metabolic stress. In renal failure, the kidneys cannot remove acid effectively, so retained organic acids increase the anion gap.
Other causes can include toxic ingestions, but the most clinically common scenarios are those above. The practical value of the calculator is that it notifies clinicians to a pattern that fits a metabolic derangement even before all confirmatory testing is complete.
In real-world assessment, a high result should lead to a search for the underlying driver rather than a focus on the number alone. The next step is to determine whether the elevation is due to hypoperfusion, insulin deficiency, kidney dysfunction, or another process affecting acid-base balance.
Reasons for Normal Anion Gap Metabolic Acidosis
normal anion gap metabolic acidosis is also known as hyperchloremic acidosis. In this state, bicarbonate is reduced or exhausted, and chloride climbs to preserve electroneutrality. The result is a reduced serum bicarbonate with a mostly stable gap.
A common cause is diarrhea, which leads to direct digestive bicarbonate loss. A further major cause is renal tubular acidosis, where the kidneys fail to appropriately acidify urine or reclaim bicarbonate, causing persistent acid-base disturbance.
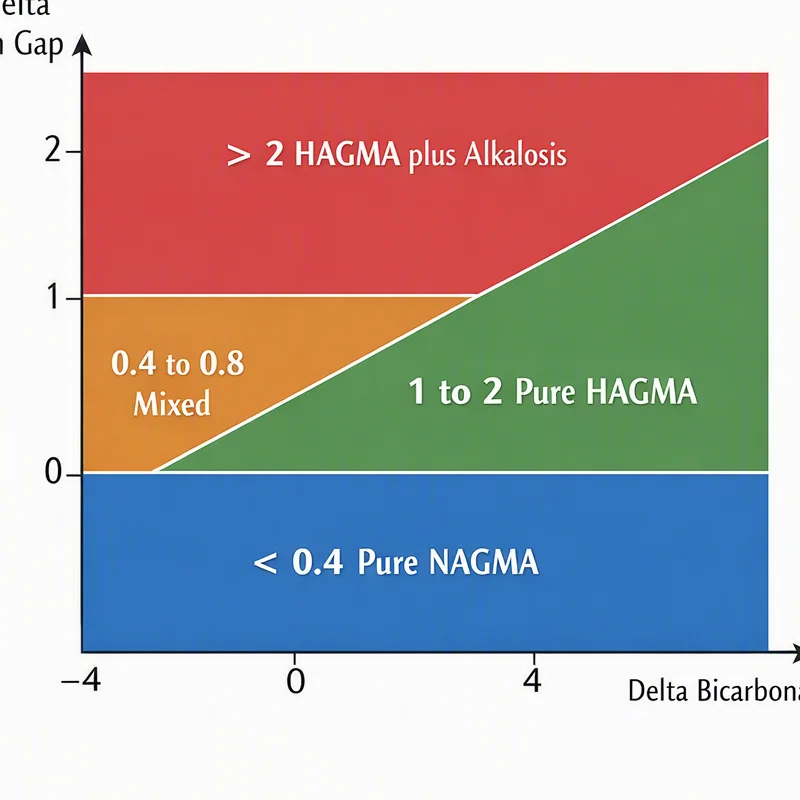
Because chloride goes up as bicarbonate declines, the measured chloride may appear markedly high. That pattern helps separate this disorder from a raised-gap process. Still, mixed disorders can occur, so the calculator should be viewed as a single part of a broader diagnostic algorithm.
In practice, recognizing hyperchloremia alongside low bicarbonate can help narrow the cause of metabolic acidosis and prevent overlooking a normal-gap pattern that needs a different workup than lactic acidosis or ketoacidosis.
In What Way Albumin Affects the Anion Gap
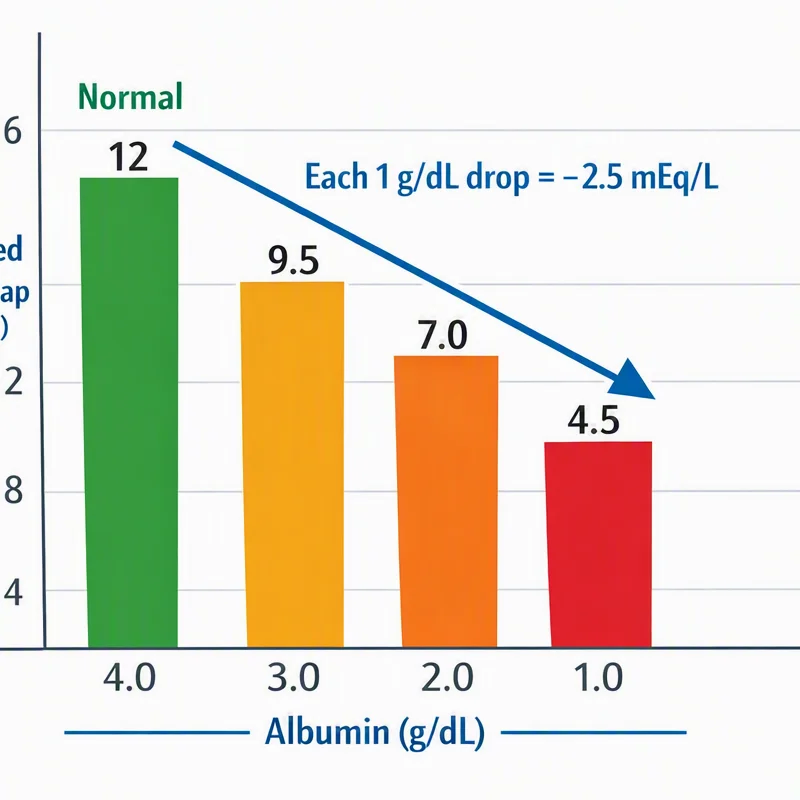
Serum albumin is a major contributor to the body’s unmeasured negative anion load. Because of that, hypoalbuminemia can lower the apparent anion gap even when acid accumulation is present. This is why albumin-corrected anion gap values are so helpful in medical interpretation.
The relationship is based in protein charge: albumin carries a negative charge at physiologic pH, so when albumin drops, the measured gap may also decrease. In patients with critical illness, low albumin is frequent, which makes uncorrected results less dependable.
Albumin correction helps clinicians prevent a false sense of confidence. A patient with sepsis, shock, or organ failure may have a “normal” raw value but still carry a clinically significant high anion gap metabolic acidosis once the correction is performed.
For this reason, many clinicians prefer using a calculator that includes plasma albumin or serum albumin as an input. That approach enhances the usefulness of the anion gap calculation as a real-world screening tool and supports better recognition of unmeasured acid burden.
Clinical Pitfalls and Common Calculation Errors
A number of pitfalls can make an otherwise useful result inaccurate. One common issue is laboratory error, including sample contamination, delayed processing, or an analyzer problem. If the result does not fit the patient’s condition, confirmation is necessary.
Another frequent mistake is failing to recognize mixed acid-base disorders. A patient may have both an elevated gap and a concurrent metabolic process that masks the expected bicarbonate change. This is especially relevant in medically complex hospitalized patients.
Potassium omission is another cause of confusion. If a calculator includes potassium and the clinician expects a sodium-only formula, the numbers will not match. Always know which anion gap formula is being used.
Unit mismatch can also distort the calculation. Input values must be in the correct units, and the calculator should not be fed values from different reporting systems without confirmation. Even small entry errors can create an incorrect impression of a major electrolyte disturbance.
Best clinical practice is to treat the calculator as one part of an acid-base analysis, not the final answer. If the result is unexpected, recheck the raw electrolytes, review the chart, and compare the trend with prior laboratory values.
When to Repeat Laboratory Tests or Perform Additional Testing
More testing is appropriate when the anion gap does not match the clinical picture, when the patient appears unstable, or when the result suggests a serious metabolic derangement. A repeat panel can help confirm whether the abnormality is persistent or due to transient variation.
An arterial blood gas is useful when you need a more complete view of acid-base status, including pH and respiratory compensation. This is especially helpful if the bicarbonate value and clinical findings do not align.
Additional specific checks may include serum lactate when lactic acidosis is thought possible, or ketones when ketoacidosis is a concern. If the history suggests ingestion of a toxin or an abnormal osmotically active compound, an osmolar gap may offer helpful clues.
Repeating the test is also warranted if there is concern about laboratory error, sample handling issues, or a changing clinical condition such as evolving renal failure. The goal is to use the calculator as a starting point for targeted workup, not as an answer.
If interpreted correctly, the tool can support timely decisions, enhance recognition of metabolic acidosis, and support a more organized response to acid-base abnormalities.
FAQ About the Anion Gap
What is an anion gap calculator used for?
An anion gap calculator is used to estimate the difference between measured cations and anions on a serum chemistry panel. In practice, it helps assess acid-base balance, identify possible unmeasured anions, and support evaluation of metabolic acidosis. It is particularly valuable as a screening tool and part of broader clinical interpretation.
What is a normal anion gap range?
The normal range depends on the laboratory method and whether the calculation includes potassium. Because of lab variation, the best comparison is the facility-specific reference range that accompanies the patient’s results. A normal number does not exclude all acid-base disorders, especially normal anion gap metabolic acidosis.
How do you calculate the anion gap?
The most common anion gap formula is sodium minus the sum of chloride and bicarbonate. Some methods include potassium. The key is to use the same method as the calculator or laboratory report and confirm the units before interpreting the result.
Why should you adjust the anion gap for albumin?
You adjust for albumin because serum albumin is a major unmeasured anion. With hypoalbuminemia, the raw gap may look falsely normal. An albumin-corrected anion gap helps reveal hidden acid retention and improves the detection of high anion gap metabolic acidosis, especially in critical illness.
What situations cause a high anion gap?
Common causes of high anion gap metabolic acidosis include lactic acidosis, ketoacidosis, and renal failure. Other causes may occur, but these are among the most common and important in practice. When the gap is high, clinicians should evaluate the underlying source of acid production or impaired acid clearance and consider additional testing if needed.