What the Anion Gap Indicates
The anion gap is a valuable value derived from a serum chemistry panel that helps clinicians evaluate electrolytes and assess acid-base balance. It is not directly measured on routine blood chemistry; instead, it is a calculated estimate that shows the relationship between positively charged and negatively charged particles in the blood.
An anion gap calculator is a useful tool for this calculation, especially when reviewing a basic metabolic panel or a broader blood chemistry panel. The result can function as a diagnostic aid when evaluating an abnormal result, particularly if there is concern for a hidden metabolic derangement.
Physiologically, blood must maintain electroneutrality, meaning total positive and negative charges stay balanced. Routine lab tests measure some ions directly, such as sodium, chloride, and bicarbonate, but they do not measure every charged particle. The difference between measured cations and measured anions creates the anion gap, which indirectly represents unmeasured anions and other residual ions.
In clinical practice, the anion gap is used for screening and interpretation rather than as a stand-alone diagnosis. It can provide clues about the underlying acid-base status, especially when paired with symptoms, medication history, kidney function, and other serum values. A normal, low, or high result each points in a different direction and should always be interpreted in clinical context.
How to Calculate the Anion Gap
The most widely used anion gap formula relies on sodium, chloride, and bicarbonate from the serum chemistry panel:
Anion gap = Sodium − (Chloride + Bicarbonate)
This formula serves as the common starting point in most settings. Some labs may use a somewhat different approach depending on the assay or analyzer, but the basic principle remains the same. The value estimates the difference between measured cations and measured anions and helps identify an anion deficit or surplus of unmeasured acidic substances.
For instance, if serum sodium is 140, chloride is 104, and bicarbonate is 24, the calculation would be:
140 − (104 + 24) = 12
That result may sit within the expected reference interval, depending on the laboratory. If using an anion gap calculator, the tool does the calculation automatically and may also help with interpretation by flagging whether the result appears typical, elevated, or low.
It is important to confirm that the values come from the same blood sample and that the numbers are consistent with the intended formula. Small differences in rounding can change the final value slightly, but they usually do not alter the overall clinical impression. What matters most is whether the result fits the patient’s blood chemistry profile.
Normal Anion Gap Range and Lab Variations
There is not one consistent lab reference range for the anion gap. The reference range can change based on the analyzer, the assay used, and whether the lab measures sodium and chloride with straightforward or indirect methods. This means a value that is normal in one lab may be slightly different in another.
In practice, the lab method matters because modern testing systems can change the expected reference interval. That is why the number should always be evaluated with the range reported by the specific laboratory rather than an assumed standard. The anion gap calculator is most helpful when it also reminds users to compare the result against the relevant lab-specific interval.
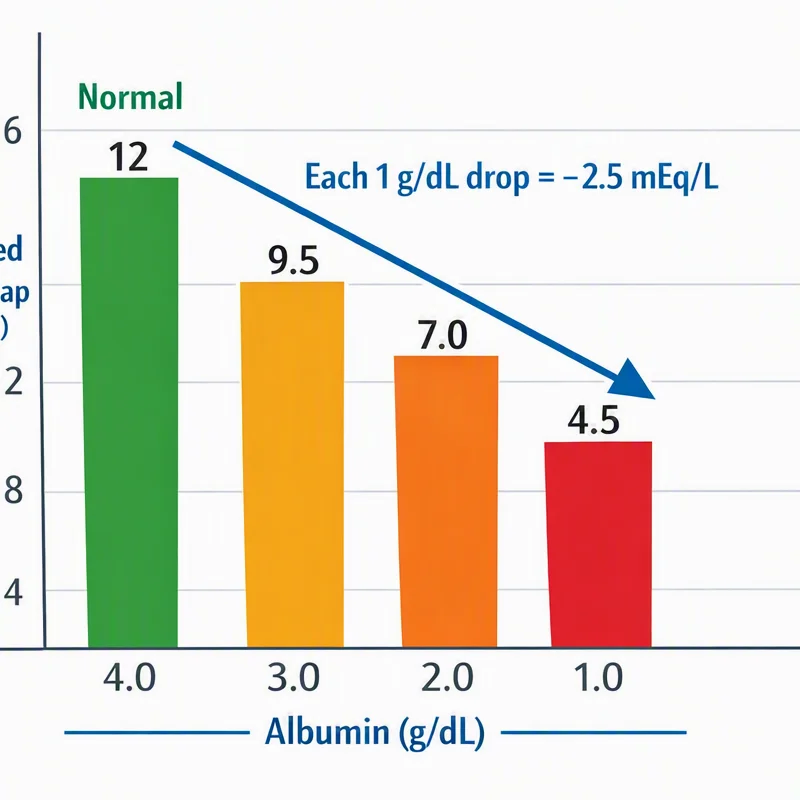
Albumin greatly affects the anion gap because it is a major unmeasured negatively charged protein in blood. When albumin is low, the anion gap can appear lower than expected even if there is clinically important acid accumulation. In those cases, a corrected anion gap can give a more accurate estimate.
Albumin correction is especially helpful when evaluating patients with low protein states, chronic illness, liver disease, or fluid overload. A corrected value better represents the true acid-base picture and may uncover hidden unmeasured anions that would otherwise be missed.
Because of these variables, the best approach is to use the anion gap as one piece of a broader physiologic assessment. A single number should not outweigh the overall clinical picture, especially if there is concern for electrolyte balance changes or another metabolic problem.
What a Elevated Anion Gap Can Mean
A raised anion gap often indicates metabolic acidosis from buildup of acids or other not measured negatively charged substances. That is why the test is often used in the evaluation of acid-base disorders. A elevated result does not reveal the cause by itself, but it reduces the differential diagnosis.
One of the most important causes is lactic acidosis, where lactate builds up when oxygen delivery or utilization is impaired. This may occur in shock, severe infection, ischemia, or other states of poor perfusion. In these cases, the anion gap may increase before other abnormalities become obvious.
Ketoacidosis is another important cause, including diabetic ketoacidosis, alcoholic ketoacidosis, and starvation ketosis. These conditions create acidic ketone bodies that increase the gap. The clinical picture often includes hyperglycemia, dehydration, vomiting, altered mental status, or a history of poor intake.
Another major category is renal failure, where the kidneys cannot excrete acid effectively. As acid accumulates, the anion gap may climb. This is a physiologic marker of impaired acid clearance and should be interpreted alongside creatinine, blood urea nitrogen, urine findings, and overall kidney function.
Toxic alcohol ingestion is a critical consideration when the anion gap is high, especially if the clinical history is unclear. Substances such as methanol or ethylene glycol can lead to severe metabolic acidosis and other dangerous findings. In these cases, time-sensitive evaluation is essential.
Other causes of high anion gap metabolic acidosis may include salicylate toxicity, advanced renal disease, and various forms of severe illness. The exact cause depends on the clinical context, symptoms, exposures, and accompanying labs. An elevated value is best seen as a clue that prompts targeted evaluation rather than a final diagnosis.
What a Low Anion Gap Can Mean
A low anion gap is not as common, but it can still be important clinically. The most frequent explanation is hypoalbuminemia, since albumin plays a major role to the pool of unmeasured anions. When albumin drops, the gap may drop even if the patient has a substantial metabolic disturbance.
Paraproteinemia is another important cause. In conditions such as monoclonal gammopathies, abnormal proteins can change the charge balance and lower the gap. This is one explanation an unexpectedly low result may lead to further evaluation for protein disorders.
Laboratory error should always be kept in mind. Sample handling issues, analyzer interference, or transcription problems can all lead to a spurious result. If the value does not fit the patient’s overall picture, repeat testing is often the best next step.
Hypermagnesemia can also contribute to a low anion gap because excess positively charged ions alter the balance. In less common cases, other cation excess states or unusual interferences may be involved. As with a high result, the low value itself is not the diagnosis—it is a signal to look for the underlying cause.
When a low anion gap is found, the first question is whether albumin is reduced. If so, a corrected calculation may bring back to normal the result or show that the low gap is mostly explained by protein loss. If albumin is normal, the differential widens and should include paraproteinemia, analytical issues, and rare causes.
How to Apply an Anion Gap Calculator in Real-World Practice
Working with an anion gap calculator in daily workflow begins with inputting the key serum sodium, serum chloride, and serum bicarbonate values from the corresponding serum chemistry panel or basic metabolic panel. The output gives a quick number that can guide next steps in clinical interpretation.
The calculator is most useful when viewed as a clinical support tool rather than a stand-alone answer. A normal value may offer reassurance that there is no obvious large-gap disturbance, while a high or low value may lead to a more detailed review of symptoms, medications, and related labs. It supports organize the thought process during bedside evaluation.
A practical approach is to ask three questions:
- Does the result fall within the lab’s expected reference interval? Is the patient’s albumin remain low enough to justify albumin correction? Do the clinical findings suggest acid accumulation, protein abnormalities, or a possible analytical issue?
If the answer suggests a high gap, consider whether the patient has signs of metabolic acidosis, including rapid breathing, weakness, confusion, or dehydration. If the answer suggests a low gap, review albumin, total protein, medication exposures, and whether a repeat sample is needed.
The calculator is also useful for trend monitoring. A changing value can reflect progression or improvement in illness, treatment response, or shifts in albumin corrected anion gap formula fluid and electrolyte status. For that reason, serial interpretation may be more revealing than a single isolated number.
Constraints of the Anion Gap
Even though it is helpful, the anion gap has important clinical limitations. It does not measure every relevant substance in blood and cannot fully characterize acid-base disorders on its own. It should be used as part of a more comprehensive evaluation, not as a replacement for other testing.
One limitation is that undetected anions vary between patients and conditions. The apparent gap may change because of albumin, phosphate, organic acids, and other ions that are not directly reported on routine panels. This means the same number can have different implications in different clinical settings.
Albumin adjustment helps address one of the biggest blind spots, but it does not solve everything. Even with correction, the anion gap may overlook subtle disorders or downplay severity when multiple processes are present. That is why clinical context remains important.
A further concern is mixed acid-base disorders. A patient may have high-gap metabolic acidosis plus a concurrent metabolic alkalosis, respiratory disorder, or other compensation that masks the typical pattern. In such cases, the anion gap is only one clue among several.
The result can also be influenced by measurement technique, interference, or unusual blood chemistry states. Because of these factors, the gap should be used as an interpretive tool rather than a definitive marker. Its strength lies in helping clinicians detect a hidden problem earlier in the diagnostic process.
When to Check Back on Irregular Results
An unexpected anion gap should warrant additional review when it does not align with the overall clinical picture or when symptoms raise concern for an time-sensitive disorder. The first step is often repeat testing to verify that the number is repeatable and not due to an lab issue.
If the result remains abnormal, a blood gas may be useful to more clearly define the acid-base disorder and assess whether respiratory compensation or another process is present. This can help determine whether the chemistry panel is showing a true metabolic disturbance and how severe it may be.
Assessment of renal function is also crucial, especially when the gap is increased or when kidney disease is considered. Creatinine, blood urea nitrogen, urine studies, and overall fluid status can assist in identifying whether reduced acid clearance is contributing to the abnormality.
A broader clinical evaluation may cover lactate, ketones, toxicology testing, serum proteins, magnesium, and other targeted studies depending on the history. The aim is not to test all possible causes, but to tailor the workup to the likely cause. If the patient appears ill, symptomatic, or unstable, abnormal results should be addressed promptly.
Even a mild abnormality may deserve attention if it represents a recent change or fits a suspicious trend. By combining the anion gap with the rest of the serum chemistry panel, clinicians can more effectively pinpoint the source of the problem and decide on the right next step.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to easily determine the anion gap from a serum chemistry panel or basic metabolic panel. It helps with interpretation of acid-base status, especially when evaluating metabolic acidosis, electrolyte balance, and possible unmeasured anions. It is a diagnostic aid, not a final diagnosis.
How do you calculate the anion gap from a serum chemistry panel?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium − (chloride + bicarbonate). These values should come from the same sample, and the final number should be compared with the lab reference range reported by that laboratory.
What is a normal anion gap range?
A typical range is influenced by the lab procedure and the specific reference range used by the laboratory. Because analyzers and assays differ, there is no one fixed value. Always compare the result to the lab reference interval provided with the serum chemistry panel.
Why should the anion gap be corrected for albumin?
Albumin is a major unmeasured anion in blood. When albumin is low, the measured anion gap may appear normal incorrectly or low even if there is a genuine acid-base disturbance. Albumin correction helps estimate a corrected anion gap and supports interpretation in patients with hypoalbuminemia.
What causes a high or low anion gap?
A high anion gap commonly suggests metabolic acidosis from lactic acidosis, ketoacidosis, renal failure, or toxic alcohol ingestion. A low anion gap is often related to hypoalbuminemia, but it can also be seen with paraproteinemia, laboratory error, or hypermagnesemia. The clinical context and repeat testing help identify the cause.